
National
Nielsen Study: Black Media More ‘Relevant’ to Black Consumers


NNPA Chairman Cloves Campbell speaks as NNPA President and CEO Bill Tompkins (left), Nielsen Senior Vice President Cheryl Pearson-McNeil (center) and Nielsen Vice Chair Susan Whiting (right) await their turn at the podium. (Photo by Roy Lewis for NNPA)
NNPA Editor-in-Chief
WASHINGTON (NNPA) – Companies that fail to advertise with Black media are missing an opportunity to effectively reach nearly 43 million African Americans whose $967 billion annual buying power is projected to exceed $1 trillion in three years, according to the new study released by Nielsen and the National Newspaper Publishers Association (NNPA).
“Still the largest racial minority group in America, with a projected buying power of $1.1 trillion by 2015, Black consumers remain at the forefront of social trends and media consumption,” the study found. The findings were released Friday at the Congressional Black Caucus Foundation Legislative Conference.
“Our collaboration with the NNPA has been successful,” said Susan Whiting, vice chair of Nielsen, a premier global information and measurement company. “NNPA’s insertion of the report into its 200 publications allows Nielsen access to millions of African-American consumers, and allows us to share vital information that will help increase the awareness of Blacks’ consumer power.”
And according to the report, that power is considerable.
“Since 2000, the total U.S. population only increased by 11.3%, while the Black population increased by 17.9%, a rate that is 1.6 times the greater overall growth,” the Nielsen study said. The report noted that the U.S. Black population is larger than 163 of the 195 countries in the world, including Argentina, Poland, Canada and Australia.
“The average income for African-American households nationwide is $47,290 with 35% earning $50,000 or more,” the report stated. Ten percent of Black households earn $100,000 or more each year. The study noted, “The Black population and its aggregate buying power is overall more geographically widespread and more diverse than other ethnic and racial segments.”
Cloves Campbell, chairman of the NNPA and publisher of the Arizona Informant, said: “Marketers underestimate the opportunities missed by overlooking Black consumers’ frustration of not having products that meet their needs in their neighborhoods. And companies that don’t advertise using Black media risk having African-Americans perceive them as being dismissive of issues that matter to Black consumers. This report demonstrates what a sustainable ad influential economic force we are.”
Benjamin Jealous, president and CEO of the NAACP, stated that African-American readers give more credence to ads placed with Black media than those that appear in the general interest publications. And the Nielsen research supports that view.
According to the report:
• Ninety-one percent of Blacks believe that Black media is more relevant to them;
• Eighty-one percent believe that the products advertised in Black media are more relevant to them;
• Seventy-eight percent would like to see more Black models/actors used in ads (51 percent said they would purchase a product if the advertising portrayed Blacks positively);
• Seventy-seven percent of African Americans said Black media has a better understanding of the needs and issues that affect them;
• Seventy-three percent believe Black media keeps them in touch with their heritage;
• Sixty-eight percent want to see more commercials directed specifically to Black audiences and
• Sixty-seven percent of Blacks want to see more advertising targeting Black consumers.
NNPA President and CEO Bill Tompkins said Black media plays a unique role in the African-American community.
“The general media does not cover us as well as we cover ourselves,” he said. Tompkins noted that Black media receives only 2 percent of the $120 billion advertising dollars spent with general media.
The top 10 companies advertising with the Black media were: 1. Proctor & Gamble ($75.3 million), 2. L’Oreal ($39.9 million), 3. McDonald’s ($34.9 million), 4. Johnson & Johnson ($27.7 million), 5. Verizon Communications ($26.3 million), 6.National Amusements ($24 million); 7. Hershey ($23.5 million), 8. Comcast ($23.4 million), 9. General Motors ($23.1 million) and 10. Berkshire Hathaway ($23.1 million).
The top 10 advertisers spent a total of $321,892,840 with African American media in 2012, up 1.99 percent over 2010. Over that same period, the largest jump in advertising was Hershey (49.16 percent), followed by McDonald’s (19.52 percent), Comcast (19.44 percent) and National Amusements (14.98 percent). From 2010 to 2011, General Motors advertising with Black media declined by 30.45 percent and Johnson and Johnson dropped by 21.17 percent.
The top advertisers by categories in the first quarter of 2012 were: 1. Automotive, 2. Quick restaurant service, 3. Motion picture, 4. Wireless telephone service, 5. Pharmaceutical, 6. Auto insurance, 7. Insurance, 8. Direct response service, 9. Restaurant and 10. Department stores. The largest increases in advertising over the past two years were insurance (118.7 percent), followed by motion picture (19.88 percent) and direct response (15.16 percent). The biggest declines were in auto insurance (34.45 percent) and department stores (12.77 percent)
The top insurance/financial advertisers in the first quarter of 2012 were: 1. Berkshire Hathaway ($6.9 million), 2. Allstate ($6.2 million), 3. State Farm ($3.4 million), 4. Progressive ($3.3 million), 5. Bancorp ($2.3 million), 6. Wells Fargo ($2 million), 7. Nationwide ($1.7 million), 8. PGC Holdings ($1.7 million), 9. Zurich Financial and 10. JLL Partners.
The top 10 restaurant advertisers in the first quarter of this year were: 1. McDonald’s ($8.2 million), 2. Yumi Brands ($3.1 million), 3. Doctors Assoc. [Subway] ($1.9 million), 4. Domino’s Pizza ($1.7 million), 5. Darden Restaurants ($1.7 million), 6. Wendy’s ($1.7 million) 7. 3G Capital, 8. DineEquity, 9. Papa John’s and 10. AFC Enterprises ($796,000).
In the first quarter of 2012, the top 10 health and beauty advertisers were: 1. Procter & Gamble ($10.9 million), 2. L’Oreal ($9.6 million), 3. Unilever ($5.4 million), 4. Johnson & Johnson ($4.4 million), 5. Kimberly-Clark ($2.4 million), 6. Pfizer ($2.4 million), 7. Estee Lauder ($2.3 million), 8. Artal Luxemborg ($2.1 million), 9. Eqyss International ($1.8 million) and 10. NAC Marketing ($1.7 million).
There were some glaring omissions from the Top 10 lists. Among banks, for example, only No. 4 Wells Fargo, with assets of $1.3 trillion, and No. 5 U.S. Bancorp, with assets of $340.12 billion, were top advertisers with the Black media. Missing from the list were: JP Morgan Chase, with total assets of $2.27 trillion, Bank of America ($2.13 trillion), CitiGroup ($1.8 trillion), Bank of New York Mellon ($325.25 billion), PNC Financial Services ($271.21 billion), State Street Corp. ($216.3 billion), Capital One ($206.02 billion) and SunTrust Banks ($176.86 billion).
Also missing from the Top 10 insurance and financial list were Liberty Mutual, Travelers Group, American International Group (AIG), Farmers, USAA, Hartford, Chubb, American Family and Met Life.
When asked why some companies are not trying to reach Black consumers through the Black media, Cheryl Pearson-McNeil, Senior Vice President for Community Relations and Public Affairs for Nielsen, said: “Some of it is that they just don’t know.” She added, “Just as you would not ignore an entire country…it’s important that these corporations have this information at their fingertips.”
In general, Blacks are more brand-conscious than other groups and have other characteristics that give them clout beyond their considerable numbers. For example, Blacks buy hand and body lotion at a rate that is 54 percent higher than the general population. They make more shopping trips than any other group and over index in such categories as mobile telephones.
The impact of African-Americans extends beyond their immediate communities. The Nielsen study cited a report from Burrell Communications that shows 73 percent of Whites and 67 percent of Hispanics believe Blacks influence mainstream American culture.
Jesse Jackson said, “It’s not so much as what we spend with these corporations, but what they spend with us in trade.”
###








Black Press
CalAIM Helped Alfred Flores Rebuild His Life. Why Can’t More Californians Access Its Benefits?
BAKERSFIELD NEWS OBSERVER — “Under CalAIM, there has been this incredible ability to pay for certain things that are helpful to anyone experiencing homelessness,” said Margot Kushel, Professor of Medicine, UCSF Director of UCSF Benioff Homelessness and Housing Initiative. “We can pay for things like street medicine. We can pay for enhanced case management, housing tenancy support services to keep people in their housing, and things like first and last month’s rent to help people.”


CalAIM offers housing and health care support through Medi-Cal, but fragmented health-plan rules, administrative barriers and limited awareness can make those benefits difficult for vulnerable Californians to access.
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship.
By Marion Apio | California Local News Fellow
California’s largest Medi-Cal transformation—California Advancing and Innovating Medi-Cal, or CalAIM—was designed to connect residents experiencing homelessness, trauma, and chronic illness directly to health care and social services. The statewide initiative allows healthcare providers to bill Medi-Cal for intensive, field-based care coordination, bringing doctors, social workers, and housing navigators directly to unsheltered residents where they live.
Yet despite CalAIM’s ambitious promise to fund care outside clinic walls, health care providers say many unhoused Angelenos still face steep barriers to accessing these services. Health plans have not always been aligned on which services to offer, creating a patchwork of coverage across the state. For patients, those differences can mean delays in approvals, changes in available services or additional paperwork before care or housing assistance can move forward.
“Under CalAIM, there has been this incredible ability to pay for certain things that are helpful to anyone experiencing homelessness,” said Margot Kushel, Professor of Medicine, UCSF Director of UCSF Benioff Homelessness and Housing Initiative. “We can pay for things like street medicine. We can pay for enhanced case management, housing tenancy support services to keep people in their housing, and things like first and last month’s rent to help people.”
“Pathways to housing are highly effective, she added, “but we need more of them. The problem is not so much that it doesn’t work for the people it’s serving; it’s that it’s under-resourced for the people it’s serving, and most people don’t get it.”
Across Los Angeles County, community organizations and street medicine teams report spending significant hours navigating complex enrollment portals and billing hurdles that delay care for residents in critical need.
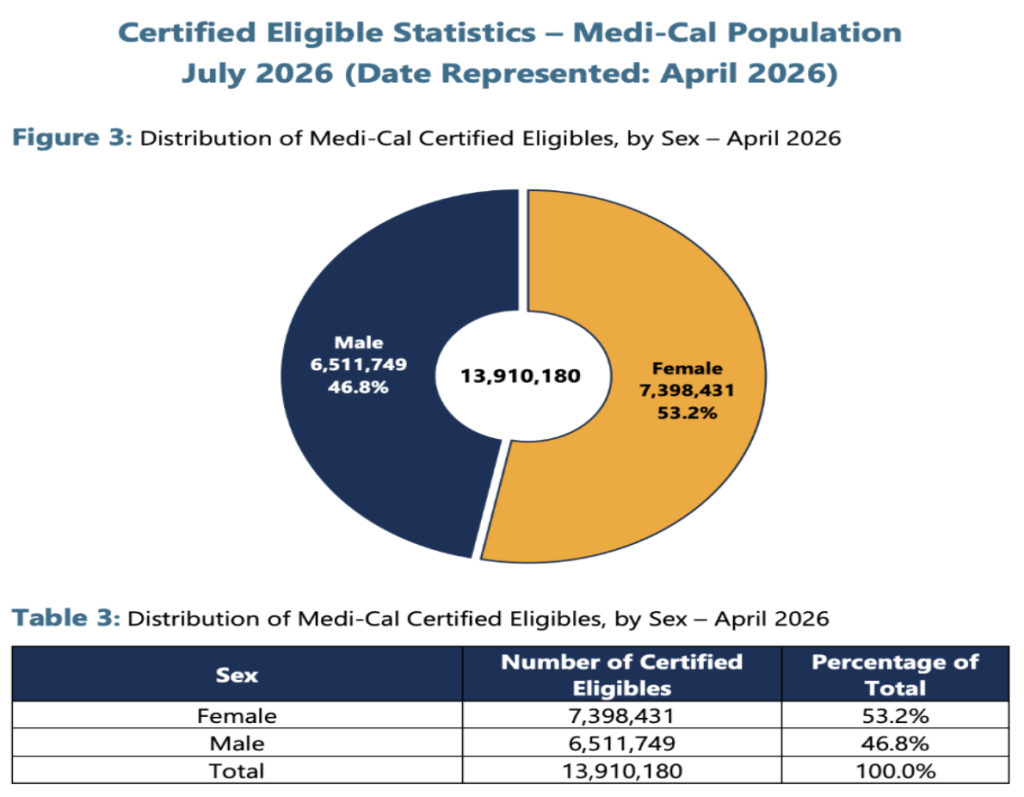
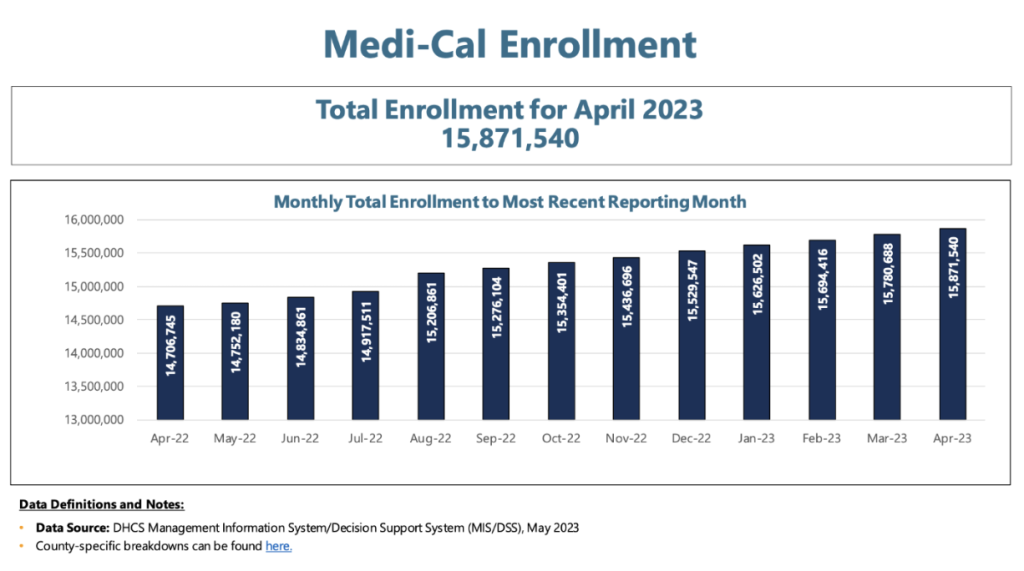
More than four years after California launched CalAIM to use Medi-Cal funding for nonmedical needs such as housing, food and case management, overall Medi-Cal enrollment has declined from about 15 million in 2023 to 13,910,180 in April 2026, according to the California Department of Health Care Services. CalAIM is not a separate insurance program and does not have its own enrollment or withdrawal process; people enroll in Medi-Cal and may qualify for CalAIM services based on their needs.
For 53-year-old Alfred Flores, connecting with a CalAIM-funded street medicine team along the Los Angeles River proved transformative.
Flores was only 17 when he first entered California’s prison system as an adult.
Raised around family members involved in gang life and without financial resources for a private legal defense, the young Flores cycled through juvenile halls and state prisons, including the California Institution for Men in Chino and a correctional facility in Delano.
“I was tried as an adult and we didn’t have any lawyers or nothing,” Flores said. “So, yeah, I was misjudged, you know. But it is what it is.”
Decades after his release, the consequences of incarceration lingered. Diagnosed with severe post-traumatic stress disorder, Flores struggled to navigate crowded public spaces and complex social service systems. Unhoused and contending with uncontrolled diabetes, his health rapidly deteriorated.
Flores’ path changed when he met Artie Vasquez, a community health worker and case manager with St. John’s Community Health. Vasquez helped Flores navigate and access medical care through case management services provided under CalAIM’s Enhanced Care Management benefit — and, just as importantly, helped him secure an apartment in Inglewood using Medi-Cal dollars.
Enhanced Care Management (ECM) — a Medi-Cal benefit that provides intensive, individualized care coordination for members with complex needs — pairs members with a care manager who coordinates physical, behavioral and social services, while Community Supports address needs such as housing instability, nutrition and chronic-condition management.

“I can go in and out of my house. I can shower whenever I want. Use the restroom whenever I want. It’s my house, you know,” Flores said.
Artie Vasquez, who overcame similar life challenges before becoming a case manager, said the program provides the scaffolding needed for individuals leaving incarceration to successfully transition back into society.
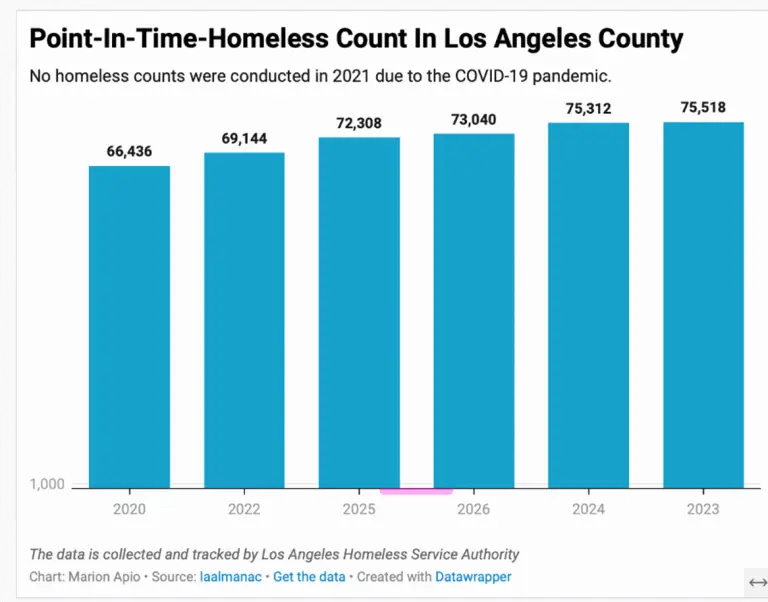
Medi-Cal covers close to 14 million residents statewide. In Los Angeles County, where over 70,000 people experience homelessness on any given night, connecting high-need populations to social safety nets remains an operational challenge.
CalAIM addresses these challenges through Community Supports, or non-medical interventions, such as move-in security deposits, housing navigation, and modifications to make housing accessible.
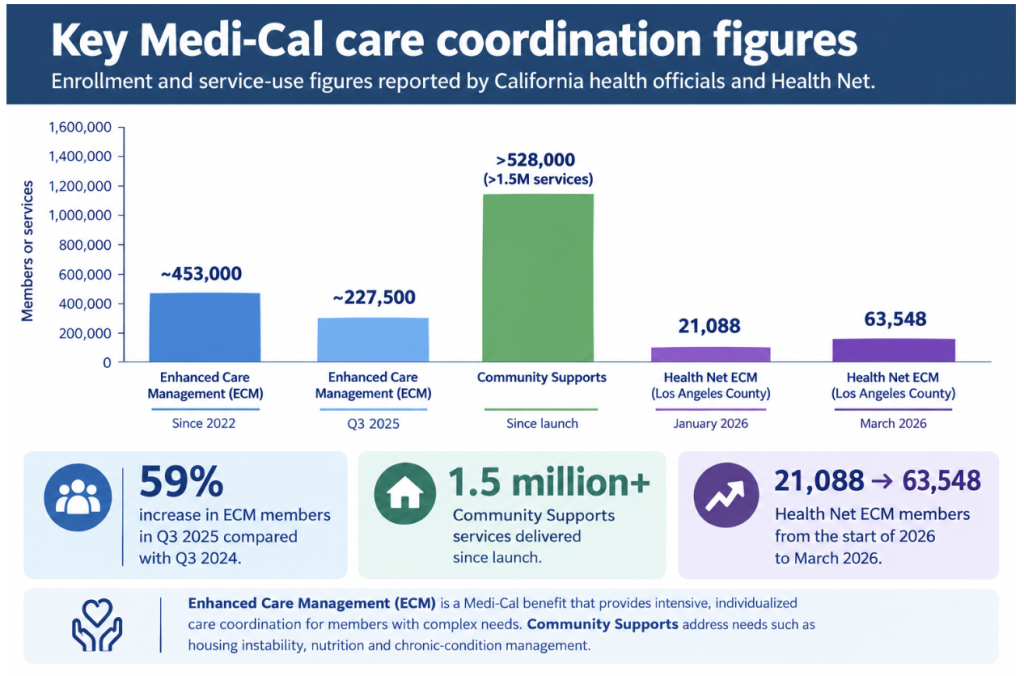
For frontline clinics, the growth in such services represents a massive shift in how care is delivered.
Christina Guevara, an Enhanced Care Management program manager at St. John’s Community Health has watched this safety-net infrastructure expand over six years.
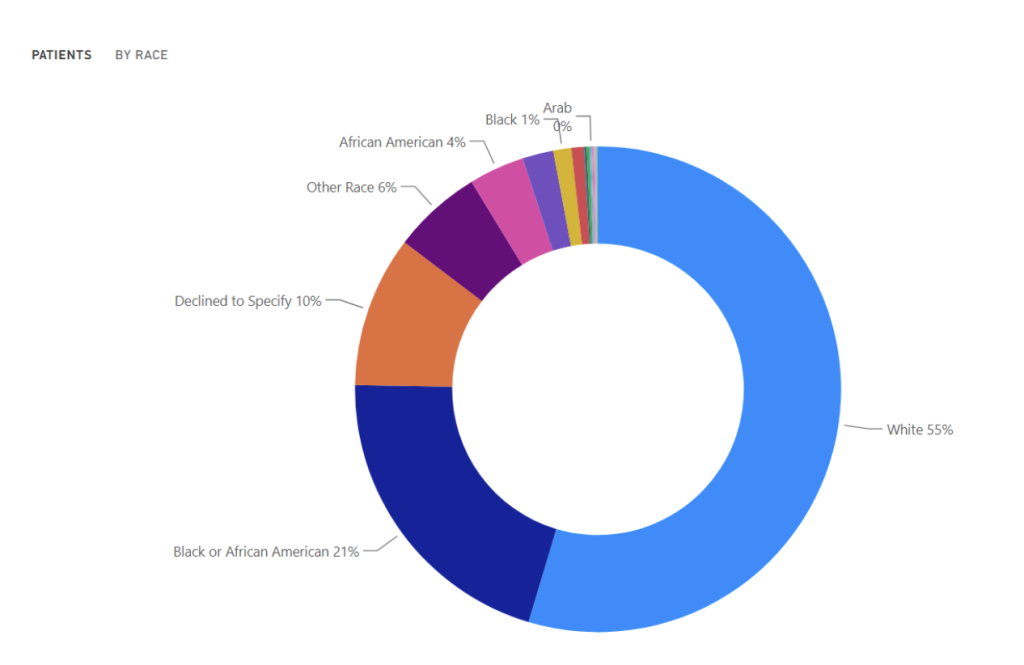
In just the past three years, St. John’s CalAIM caseload has surged from under 1,000 patients to nearly 1,600, serving a community that is roughly 55% Latinos and White as well as 26% Black, according to Monica Cotom, director of CalAIM at St. John’s Community Health.
Guevara noted that language barriers, low health literacy, and a lack of support systems frequently cause low-income patients to drop out of care. She said that is especially true for older patients who may struggle to navigate complex medical instructions or question a doctor’s diagnosis.
In one instance, St. John’s case managers worked with an unhoused domestic violence survivor living in a shelter who avoided medical visits out of fear of being located by an abuser. Through biweekly phone calls, virtual support groups, and accompanied clinic visits, case managers helped the survivor secure permanent housing and reduce his hemoglobin A1C level from a dangerous 14% down to 7% over an 18-month period.
Yet, administrative breakdowns regularly interrupt patient care.
“The health plans have never been quite aligned for this program across the board, and so that’s been the barrier,” said Cotom. “We have to fluctuate with whatever the health plans need, and so that makes it hard.”
Because each Medi-Cal managed care plan operates with its own documentation requirements, billing systems, and approval rules, caseworkers must constantly adapt to conflicting administrative processes. For unhoused patients, these hurdles translate directly into real-world delays. For unhoused clients, bureaucratic errors can pause housing placements for months.
In Inglewood, city officials acknowledge that awareness remains a barrier.
Roberto Chavez, HUD programs manager for the City of Inglewood, called CalAIM an “untapped resource,” and noted that municipal governments currently lack public education campaigns to connect eligible residents with the state program.
“Not too many people are aware of that,” Chavez said. “Again, that requires some education of the residents and people experiencing homelessness, as well as any staff that’s in charge of identifying resources.”
When asked what the city is doing to publicize CalAIM to unhoused residents, Chavez said the city relies on partner non-profits rather than municipal outreach.
“Nothing at the current moment,” Chavez said. “But we direct folks to the St. Margaret’s Center, and they make folks aware of the CalAIM program, as well as the South Bay Cities Council of Governments.”
Addressing why local agencies struggle to roll out CalAIM seamlessly, Kushel called it a nearly impossible task.
“When you’re frantically trying to plug up holes from 50 years of failed policies at every level of government in a wildly unequal country where there’s rampant income inequality … it’s also really an impossible task,” Kushel said, adding that local authorities are “trying to put fingers into sort of a leaking bucket, and it’s very hard to do that.”

Ashley Watson was offered CalAIM services in June 2025 while living in her car in Los Angeles. Working with Stephanie Ortiz, a case manager, Watson secured several jobs to raise her monthly rental budget from $1,200 to $2,000. When bad credit led to apartment rental rejections, Ortiz assisted in securing a guarantor.
However, during the application process, an administrative error caused Watson’s Medi-Cal coverage to terminate unexpectedly. It took nearly a month of staff effort to restore her coverage before security deposit and move-in funding could be released. Watson moved into her apartment in November 2025 and officially graduated from the program in June 2026.
Mary Vargas, Community Supports program manager at St. John’s, said administrative gaps leave the most vulnerable clients behind.
“A lot of people don’t understand why and feel powerless in their own care,” Vargas said. “If you’re powerless, have a chronic condition, and are alone with no support, your health significantly declines.”
Guevara reported that rising fears around immigration status and potential scams have led members to decline home visits or ignore phone calls from case managers. To support clients facing these anxieties, St. John’s transitioned many in-person check-ins to virtual appointments.
DHCS acknowledged that some immigrant families are experiencing fear about data-sharing with federal agencies that might use the information in enforcement actions. The department said it does not track whether people decline CalAIM services because of those concerns, but encouraged eligible Medi-Cal members to maintain their coverage and continue seeking care.

Vasquez noted that individuals released from state prisons face delays of 30 to 90 days before their active Medi-Cal status is reinstated.
Those delays force clinics to rely on sliding-scale fees based on income –which many newly released participants do not have –while unhoused individuals without physical addresses often rely on family members’ addresses to keep their mail delivered and avoid losing coverage.
But for those who get past the hurdles and receive services, the results can be life changing.
Flores is now enrolled in online business and culinary arts classes through Coastline College, working toward his long-term goal of financial independence.
“Before, I didn’t know how to go about things, but now with my medication, my doctors, and my case manager who always calls to see if I’m doing okay, it has helped me a lot—and I can trust the system,” Flores said.
Black Press
How Inglewood’s Homeless Seniors Are Finding Relief Through Housing and Trauma-Informed Care
BAKERSFIELD NEWS OBSERVER — For people like Gilbert Ramirez, the dangers of living on the street compound with age. Chronic illnesses become harder to manage, mobility declines and minor health problems can quickly escalate into medical emergencies without a stable place to recover or store medications. Increasingly, this vulnerable population includes seniors falling into homelessness for the first time after a lifetime of low-wage, physically demanding work.
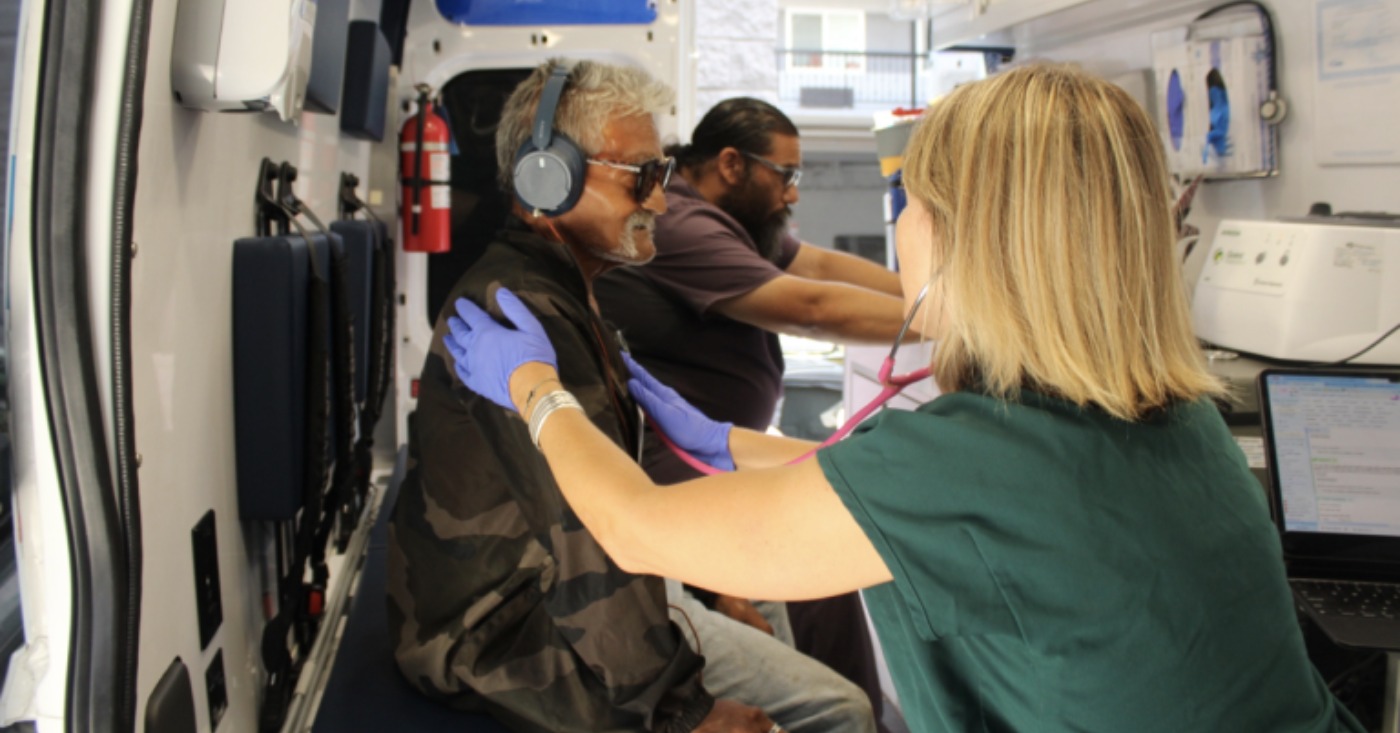
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship.
For 70-year-old Gilbert Ramirez, the intersection of medical care and supportive housing proved lifesaving.
First sent to prison at 25, Ramirez spent decades cycling through nine separate sentences and three decades of parole supervision before finally completing parole seven years ago.
“I’ve been told what to do, man, for all my adult life,” Ramirez said. “I had nine turns on one number, and finally they gave my life back. So now I’m a free citizen.”
While incarcerated, he and his wife separated. After returning to society, he lost his daughter to cancer, was shot, and was left partially paralyzed and unhoused.
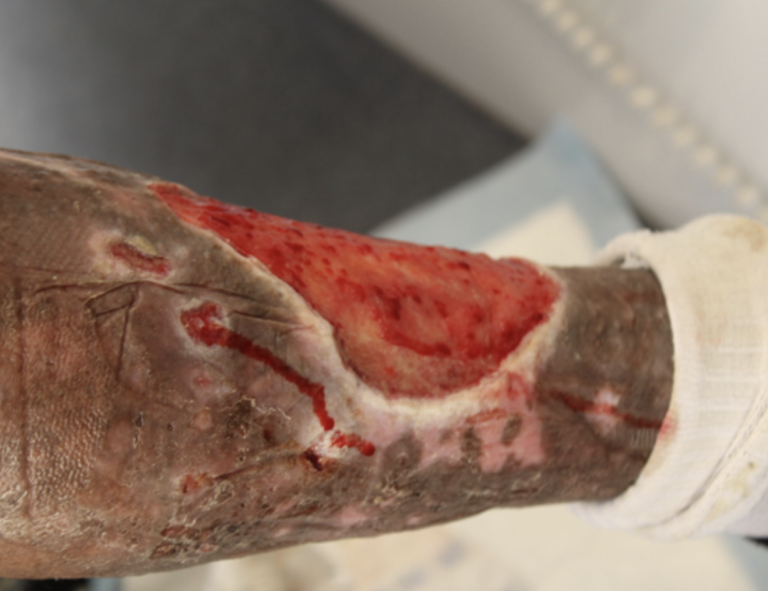
Surviving on the street, Ramirez fell into a heavy fentanyl addiction. For seven years, severe, open wounds flared on both of his legs—wounds he had no way of healing while living unhoused.
As the infections worsened, his weight plummeted to 95 pounds.
Compounding challenges for seniors who are unhoused
For people like Ramirez, the dangers of living on the street compound with age. Chronic illnesses become harder to manage, mobility declines and minor health problems can quickly escalate into medical emergencies without a stable place to recover or store medications. Increasingly, this vulnerable population includes seniors falling into homelessness for the first time after a lifetime of low-wage, physically demanding work.
“We have a large proportion of seniors experiencing homelessness—about 43 percent who had never been homeless before after the age of 50,” said Margot Kushel, professor of medicine, UCSFDirector of UCSF Benioff Homelessness and Housing Initiative
Eight months ago, outreach workers with People Assisting The Homeless—a nonprofit housing and social services agency—moved Ramirez into the Los Angeles Inn in Inglewood. They did so under an L.A. County-led initiative that brings unsheltered residents indoors by placing them inmotels converted into interim housing. It also connects clients with wraparound healthcare and case management.The effort primarily receives funding through L.A. County’s Measure A sales tax, which aims to create a direct pipeline from street encampments to permanent housing.
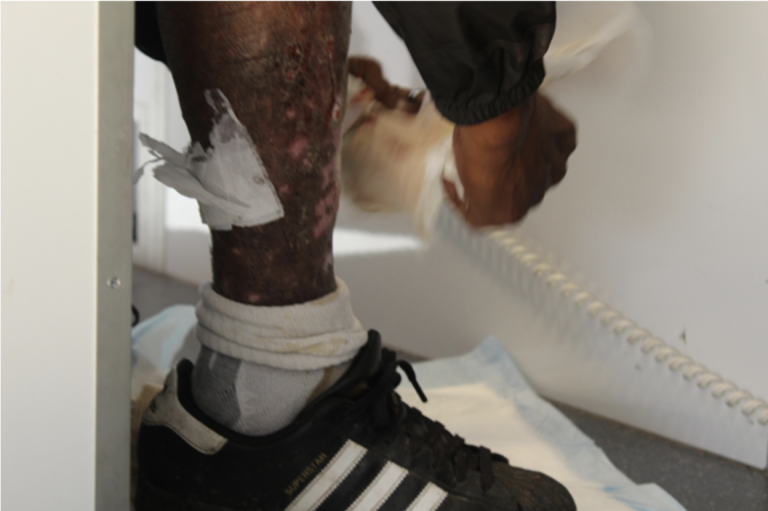
By the time Ramirez connected with Carrie Kowalski last November, a senior physician assistant with Venice Family Clinic, the wounds on both of his legs were deep, painful, and itchy. Kowalski cleaned and wrapped the wounds and provided Ramirez with naloxone nasal spray—an emergency overdose reversal drug – along with fentanyl test strips and buprenorphine starter supplies, a medication used to treat opioid addiction.
“It’s good, I ain’t now underweight,” Ramirez said about the services he receives under Pathway Home. “They offer me medicine. They come and, you know, give you everything. Whatever I need—a doctor, food, a bed, water, and everything I never had before.”
From August 2023 to August 5, 2026, Pathway Homehad moved 2,361 people into interim housing, while 892 had moved into permanent housing, according to Los Angeles County. The county said the biggest barrier to moving people from interim to permanent housing is the shortage of affordable permanent homes.
Pathway Home’s mission is to reach encampments throughout L.A. County and link people to permanent housing, said Courtney Reed, associate director at PATH.
“We operate in what we call a trauma-informed care model,” Reed said.

The Los Angeles County’s Pathway Home budget for fiscal year 2026-27 is $59.5 million. The funding includes $24.4 million from Measure A, $19.8 million in Measure H carryover, $13.8 million in state Encampment Resolution Fund carryover and $1.5 million from the county Department of Mental Health, according to information provided by the county in an email. In April 2024, the county also received a $51 million grant from the state of California to expand the Pathway Home program.
Countywide, the number of unhoused adults ages 55 and older rose nearly 5 percent, from 18,212 in 2025 to 19,104 in 2026, accounting for about 26% of the county’s 73,040 unhoused residents. Black residents continue to be disproportionately represented among the people experiencing homelessness, accounting for 21,822 people of the unhoused population within the Los Angeles Continuum of Care, according to the 2026 Greater Los Angeles Homeless Count.
A shortage of affordable housing has limited options for the unhoused in Inglewood
In Inglewood, Pathway Home teams have moved 54 people into temporary housing in motels, according to the mayor’s office. While experts call this placement critical for vulnerable seniors, city officials clarified Inglewood is strictly a logistical partner.
“We have no funding obligation, Pathway Home Initiative is funded by the County of Los Angeles,” said Roberto Chavez, Inglewood’s HUD programs manager. “The city is a partner.”
However, transitioning people into permanent housing has also become more difficult in Inglewood, where the city’s housing voucher program is frozen under a “designated shortfall” from the U.S. Department of Housing and Urban Development because federal funding failed to match local rent increases.
“The housing authority has spent its annual allocation, and HUD is monitoring our finances,” Chavez said. “The result is we’re not able to issue more vouchers to families to get housing.”
While homelessness continues to trend downward in Inglewood—where the unsheltered population dropped from a peak of 751 individuals in 2022 to 290 in 2026—countywide data masks a growing crisis among older and Black residents.
Challenges for seniors who are unhoused
By the time outreach workers connected with Jacqueline Thomas last November, the 67-year-old was hauling an oxygen tank across La Brea Avenue while managing a heart condition, chronic obstructive pulmonary disease, diabetes, and a daily regimen of 13 prescription pills—all while living out of her car.

A 1976 graduate of Inglewood High School, Thomas’s life unraveled a decade ago after she lost her job. Faced with fixed income limits and rising housing costs across L.A. County, strain over rent money eventually frayed family ties, leading her to choose the streets over an unstable living situation.
For 10 years, Thomas parked her car outside businesses along La Brea Avenue to sleep. She let other unhoused neighbors stay inside with her for protection, but she could not avoid constant street harassment and theft. During one incident, someone stole $1,000 from her on the sidewalk.
A decade of exposure took a permanent toll on her body.
“All these health issues I have now, I didn’t have,” Thomas said. “I got them all out here in the streets.”
Six months after moving into a private room through Pathway Home, Thomas finally has reliable electricity to power her oxygen machine and blood pressure monitor, store her heart medication in a refrigerator, and manage her health.

“Housing is an intervention to help with vascular problems—like leg swelling and open wounds from sleeping sitting up—because now our patients have a bed to elevate their legs and sleep,” said Kowalski, who has operated a mobile clinic van since December 2020. “From a medical standpoint, we can provide care, but housing is the key intervention to actually get people better.”
Homelessness advocates point to L.A. County’s high cost of living and the severe gap between fixed disability payments and local rents as key drivers fueling the region’s homelessness crisis.
In an emailed statement, the Inglewood Mayor’s Office cited the shelter operation at Hollywood Inn Suites, a converted motel on Century Boulevard, as a key local success in resolving encampments.
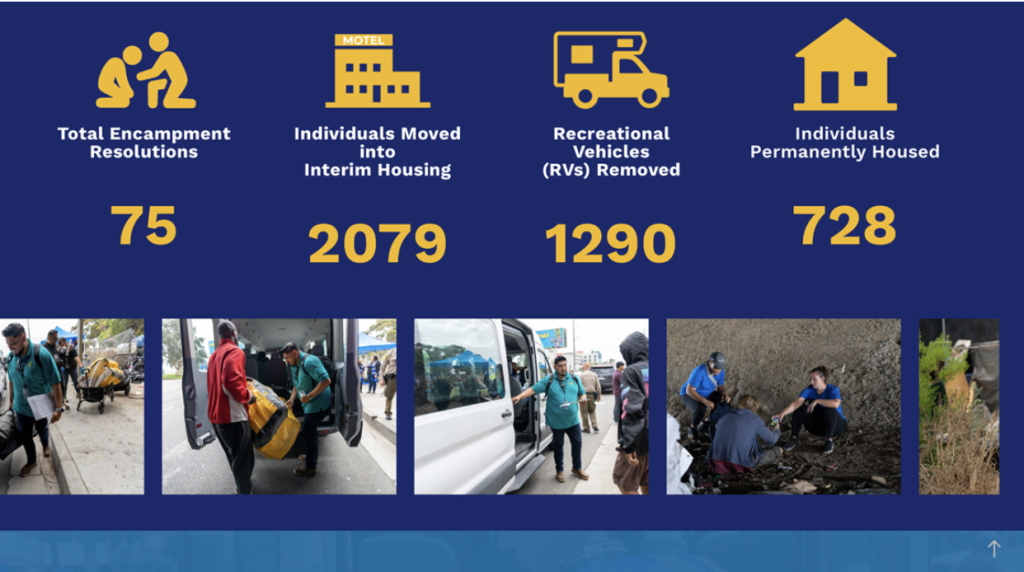
The city said its Pathway Home partnership with Los Angeles County housed 54 people who had been living on the streets. It is also exploring motel master leasing and said it would consider adding a homeless services coordinator, funded through Los Angeles County’s Measure A, in June 2026.
When discussing the types of housing initiatives like Pathway Home that place seniors into interim housing, Kushel emphasizes that a standard apartment is not enough since older adults need specific physical adaptations.
“A lot of the issues we’re having is just the physical design of whether there’s infrastructure for people who can’t climb stairs,” Kushel said. “There’s a physical design aspect like, are there grab bars, non-slip surfaces and night lights.”
For Ramirez and Thomas, moving off the streets into stable housing has allowed them to focus on long-term recovery, healthcare, and personal goals.

Ramirez, who rides his bicycle up to 100 miles a week, said he is rebuilding his strength while gathering the medical records needed to secure a housing voucher for a local senior complex through Pathway.
His dream is to one day reunite with his 23 grandchildren and 12 great-grandchildren.
“I just want to be with my grandkids, raise my great-grandkids, and jam with them, you know what I mean?” Ramirez said. “Being out on the street was rough, just fighting all the time. But since I’ve been here, you know, it’s been all right. I’m home.”
For Thomas, months inside interim housing under Pathway Home have provided a secure environment to manage her health. With her medical needs finally managed and her daily living environment secure, she is now looking toward the future—hoping to acquire a computer and take tax preparation courses to build new job skills.
It is a sharp departure from her years spent struggling just to survive on the streets.
“I’m not a hopeless case,” Thomas said. “This is just my new way of living, and I’m adjusting to it.”
Marion Apio
Marion Apio is a multimedia journalist from Uganda currently based in Inglewood reporting for the Observer Group Newspaper of Southern California in Los Angeles. She pursued journalism to make information more accessible—especially for underserved communities like the one she grew up in. Her reporting focuses on access to basic resources necessary to advance human rights, education, health and with a strong interest in solutions journalism that highlights working models addressing community-level challenges.
She is a California Local News Fellow, USC California Health Equity Fellow and Widening the Pipeline Fellow with National Press Foundation. Marion has reported for Richmond Confidential, Oakland North, Bloomberg, and has also worked with the Investigative Reporting Program at UC Berkeley on issues related to journalist safety and human rights.
Black Press
Street Medicine Brings Care to Unhoused Angelenos — But Housing Remains the Missing Prescription
BAKERSFIELD NEWS OBSERVER — Mobile street medicine teams treat the immediate health needs of the unhoused, but barriers to care, trauma, stigma and housing costs can leave the underlying causes of homelessness unresolved.
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship
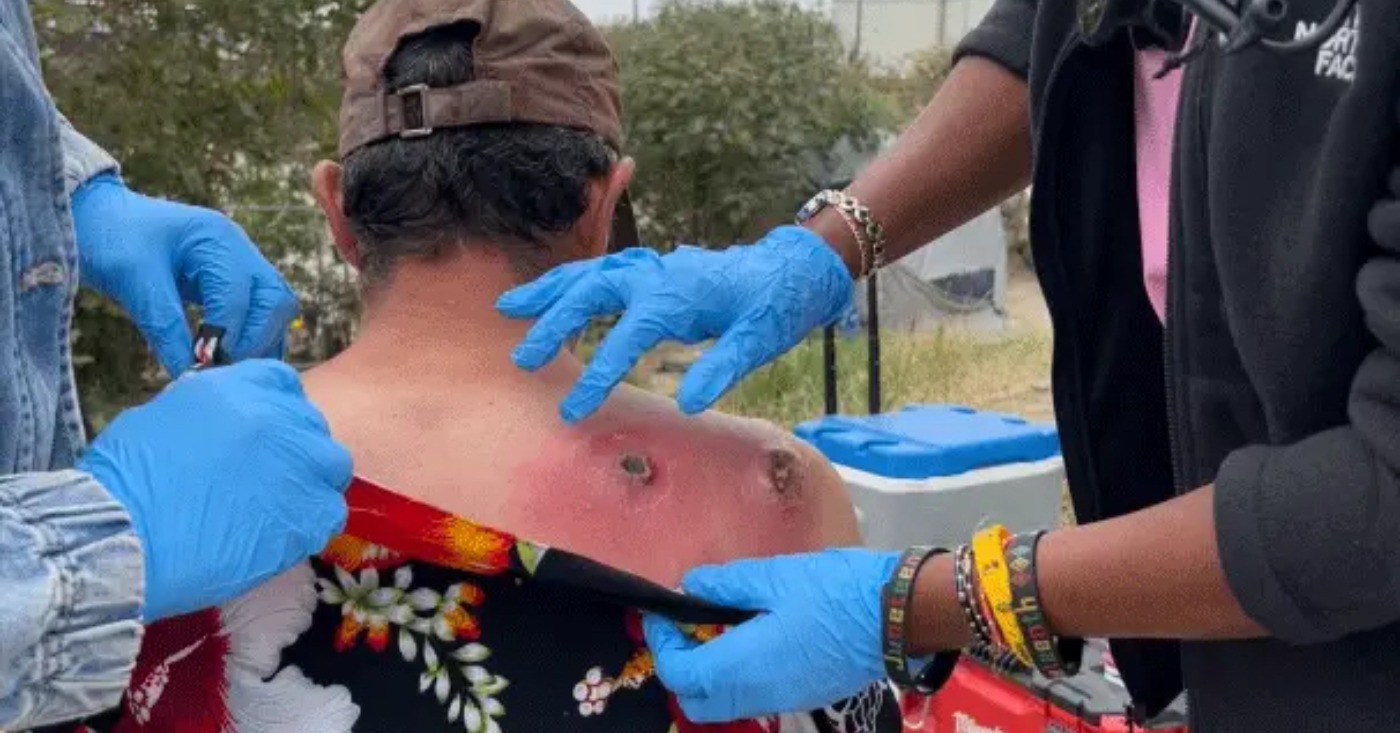
By the time a street medicine team met Alfred Flores last June along the Los Angeles River , two spider bites on his back had swollen with infection,untreated for three days.
Los Angeles News Observer
LA news from the Black press.
The stories Black Angelenos need, from people who live here. Free every Thursday.
Get the LANO Weekly
Free weekly newsletter. Unsubscribe anytime.
Divorced a year ago, the 53-year-old had been living along the riverbank for three years without a car or phone, making it difficult to connect with housing programs or reach a doctor as the infected wounds worsened with redness, heat, pus and pain.
On her weekly outreach along the L.A. River, Bukola Olusanya—a nurse practitioner and a street medicine provider with St. John’s Community Health—examined Flores on-site and wrote a prescription for antibiotics.
“My wound is infected,” Flores said in Spanish through an interpreter. “It is normal to be bitten by a spider in this area but I need help finding a home.”
Flores’s experience highlights the steep barriers to receiving housing support and providing medical care among people experiencing homelessness in Los Angeles. Many cannot access care because of physical or mental health conditions, or can’t connect to housing programs because they often lack a phone.
Traditional health care systems often require patients to have transportation, identification, a safe place to store medications and the ability to make follow-up appointments — barriers that can be difficult to overcome for people surviving on the streets.

Street medicine helps people whatever their circumstances
Street medicine challenges the traditional notion that health care must begin inside a medical facility, extending services to those in non-traditional settings and in urgent need.
These teams shift the delivery model by bringing health care directly to patients on the streets, rather than waiting for them to seek treatment in hospitals or clinics. They provide critical care that can stabilize health conditions while helping patients connect with benefits, housing and other services.
Jessica Sanchez, director of the Street Medicine team at St. John’s Community Health, said the program receives about $500,000 annually from L.A. Care Health Plan, $365,000 from the Federal Health Resources and Services Administration and $100,000 from the Los Angeles County Department of Public Health. The team also bills Medi-Cal for eligible medical services, though not all patients are insured or eligible for reimbursement.
Sanchez said the program’s grants typically run for three to five years, providing funding stability. The “street medicine initiative is not currently facing a funding threat,” she said.
Since 2023, St. John’s Community Health—a network of non-profit, federally qualified health centers—has deployed a multidisciplinary street medicine unit in Los Angeles. The mobile vans are staffed by a nurse practitioner, a medical assistant, a health benefits counselor, a community health worker, a behavioral health clinician, a substance abuse counselor and a driver.
The teams provides primary care, behavioral health, and benefits enrollment on the streets, reducing administrative hurdles to head off medical emergencies and reach unsheltered patients.
Primary care and connections are what street medicine can do best
The teams work Monday through Friday and serve around 320 patients a month.
They treat acute wounds, manage chronic conditions like diabetes and hypertension, conduct field blood draws, dispense medications, and connect patients to housing resources through the Los Angeles Homeless Services Authority’s Coordinated Entry System.
“Three years ago when we had just started street medicine it was with one team and one provider,” Olusanya said. “But with the increasing demand—especially after COVID—the team doubled everything.”
Deploying two teams is not enough without building trust with unhoused patients, Olusanya said, a lesson she learned on the beat.
While street medicine often can stabilize chronic conditions on the pavement, clinicians stress that field care is a vital shield, not a permanent solution. Without a locked door or a refrigerator to store insulin, medical intervention only acts as a Band-Aid while patients remain trapped in what can be seemingly endless housing queues.

Tanny Hernandez, 45, and her husband, Benwell Hernandez, 35, spent over three years living on the streets. They are now living in a temporary shelter in downtown Los Angeles.
Struggling to manage diabetes without refrigerated insulin
Until they encountered the St. John’s street medicine team, Tanny struggled to manage diabetes without a refrigerator to store her insulin, along with experiencing grand mal seizures and bone disease that forced her to use a wheelchair.
“My sugar levels were crazy—I mean, in the 400 range,” Tanny said. “I can’t be in direct sunlight, so I mean, everything was bad and it was going downhill.”
The American Diabetes Association recommends a premeal blood glucose target of 80 to 130 mg/dL for most nonpregnant adults with diabetes.
When unsheltered Angelenos seek traditional hospital care, they often face health struggles while navigating trauma from administrative hurdles and aggressive security in environments that can feel hostile rather than welcoming.
“While it may be tempting to think that mental health disorders or substance use cause homelessness, there is stronger evidence that the reverse is true,” said Kathryn Leifheit, an assistant professor of Health Policy and Management at the University of California, Los Angeles. “When people become homeless, housing insecurity causes severe mental strain that worsens health conditions over time.”
Homelessness remains at a crisis level in Southern California, mirroring national trends, Leifheit said. The insufficient supply of affordable housing puts many people at risk.
A rent increase can tip people already in crisis into homelessness, experts say
“When rents are high relative to incomes, any economic shock, life event, sudden illness or major bill can put someone at risk of becoming homeless,” Leifheit said.

This crisis carries a stark racial dimension. Black residents make up less than 10% of Los Angeles County’s population but accounted for about one-third of people experiencing homelessness in the Los Angeles Continuum of Care’s 2026 count, according to the Los Angeles Homeless Services Authority. The Continuum of Care is a federally designated network that coordinates homeless services and housing programs.
The count identified 21,822 Black people experiencing homelessness. Street medicine is an important way to access care for unhoused people of color, with 25% of street medicine patients identifying as Black and 23% identifying as Latino, according to the California Health Care Foundation.
“Black Americans have much lower family wealth and they’re much less likely to own their house because of redlining,” said Margot Kushel, Director of the UC San Francisco Benioff Homelessness and Housing Initiative. She points as a key contributor to “generations and generations of anti-Black racism and other ways to extract Black Americans out of the home ownership market.”

When Rayshawn Whittenburg, a 20-year-old Black Angeleno, encountered Olusanya and her team, she had spent six months on the streets with a high-risk pregnancy.
She was under the team’s care before her newborn inhaled amniotic fluid at birth, sending the infant to neonatal intensive care for two weeks. The baby was later released from the hospital into the care of Whittenburg’s mother.
“A stark racial dimension” to homelessness for Black Angelenos
Whittenburg’s experience highlights the severe maternal health disparities documented across Los Angeles County, where Black mothers and infants experience disproportionately high rates of life-threatening complications and mortality. For those surviving on the street, homelessness adds severe environmental stress and care delays to an already perilous baseline.
Whittenburg said she returned to the streets after losing her interim housing placement at the Los Angeles Inn because she did not realize that failing to remain continuously at the shelter would cost her a bed.
“I really keep to myself most of the time,” Whittenburg said. “I don’t really like people because it’s always drama.”

Olusanya noted that unsheltered patients routinely face judgment from healthcare providers based on their appearance or assumptions about drug use – preconceived notions she pushes back against, as most of her patients are not on the street because of addiction.
“One huge misconception is that unhoused folks are also inherently dangerous,” said Carol Ross, assistant director of Santa Monica outreach for The People Concern, a nonprofit that provides housing and supportive services. “Statistically speaking, folks with serious mental illness are much more of a danger to themselves than to others.”
After seven years of sobriety, Teff Ejigu, 37, is back on the streets navigating severe health and housing challenges.
Ejigu, who describes himself as a political science graduate, said he became unhoused after past triggers contributed to a relapse. He lost his housing six months ago and currently lacks a phone and essential documents to access benefits or housing such as a state ID and Social Security card.
“You know, we can’t give up,” Ejigu said. “I’m hoping that after I get back on my feet, I’ll be able to use this place as a launching pad to restarting my career and getting back to school.”

Navigating housing applications can be complicated and stressful
Beyond missing paperwork, navigating public benefit systems requires administrative literacy.
“There are resources out there, but you have to speak a special language to fill out all these forms,” Ross said. “People who don’t access public benefits have no idea how challenging it is. It’s like a full-time job.”
The main operational challenge for street medicine teams remains patient follow-up. Without phones or fixed addresses, patients are frequently lost to care, especially when encampments are cleared by the city. Olusanya said clinicians also encounter administrative barriers when trying to connect patients with services
Ross noted similar systemic limitations when patients face acute conditions, describing one unhoused individual struggling to receive cancer treatment—a case far more complex than treating a spider bite.
“In terms of getting folks connected to primary care, it works well, but there’s a lot of work to do in terms of linking people to higher levels of care,” Ross said.

“There’s definitely a need to be sure that street medicine is age friendly, that it has the workforce trained to deal with the unique needs of older adults…” Kushel said.
Local leaders should foot the bill for more street medicine teams, providers say
Some providers say city and county leaders could do more to strengthen mobile street units and cut red tape for permanent housing placements.
The Inglewood mayor’s office said the city is using federal, state and local funding to support affordable and supportive housing, including project-based vouchers and permanent supportive housing.”
The city said it is tracking 600 affordable units in various stages of predevelopment and monitoring about 46 existing density-bonus affordable units.
Roberto Chavez, HUD programs manager for the City of Inglewood, said the city is not equipped or funded to deploy mobile medical responses directly.
“I don’t think the city is equipped to deploy those resources because that’s more a function of the county or the state,” Chavez said. “We don’t have street medicine workers. That’s not something we receive funding for.”
Chavez noted that federal funding constraints continue to impact municipal budgets as housing costs outpace federal allocations.
“Every year costs go up for housing, right, and so the budget authority that we’re allocated from the federal government is not keeping up with that allocation,” Chavez said.
Off the streets, the next hurdle is going from temporary to permanent housing
The transition from temporary beds to permanent housing remains a challenge across the region. Across Los Angeles, the county identified the shortage of affordable permanent housing as the biggest barrier to moving people from interim to permanent housing.
“Healthcare is a human right. Just because somebody is living in an alley doesn’t mean that they don’t deserve to have a doctor who understands them,” said Ross.
“We only see some of them once or twice a week, so that’s the gap that we have,” Olusanya said of unhoused patients. “Cities have a bigger role to play. They have to provide the safety net that is needed by residents.” Health experts said when consistent clinical rapport and trust are established, street medicine can serve as a vital bridge to care.

“Street medicine doesn’t end homelessness. It is trying to keep people alive and safe while they’re homeless,” Kushel said. The street medicine team continues to care for Tanny and Benwell Hernandez, who live in temporary housing in downtown Los Angeles through the Inside Safe program. When Tanny cannot reach a pharmacy, the team delivers her medication directly to her door.
Regular health care “saved us,” one newly housed patient says
Benwell is studying to become a peer educator while the couple works to secure permanent housing. Still, their future remains uncertain.
Tanny said her biggest fear is waiting in temporary housing for six months only to end up back on the street.
Unlike patients living on the riverbank or sidewalk, Tanny can now benefit from reliable follow-up care because she now has a fixed address.
“We were at the point of giving up, but this program saved us,” Tanny said. “With what they do for me, my whole body—like my internal system—feels like it’s slowly getting better.”
Marion Apio
Marion Apio is a multimedia journalist from Uganda currently based in Inglewood reporting for the Observer Group Newspaper of Southern California in Los Angeles. She pursued journalism to make information more accessible—especially for underserved communities like the one she grew up in. Her reporting focuses on access to basic resources necessary to advance human rights, education, health and with a strong interest in solutions journalism that highlights working models addressing community-level challenges.
She is a California Local News Fellow, USC California Health Equity Fellow and Widening the Pipeline Fellow with National Press Foundation. Marion has reported for Richmond Confidential, Oakland North, Bloomberg, and has also worked with the Investigative Reporting Program at UC Berkeley on issues related to journalist safety and human rights.
Black Press
OP-ED: Washington Has a Chance to Save Veterans’ Lives
BLACKPRESSUSA NEWSWIRE — I became paralyzed watching young Marines go outside the base, thinking about their families and whether they would see them again. I began hallucinating that wounded Marines I cared for were walking toward me in the war zone. I now recognize that, alongside my own PTSD, I was carrying secondary PTSD from caring for wounded Marines.

I graduated from Marine Corps boot camp a couple weeks before September 11, 2001. I had no idea how profoundly 9/11 would change the trajectory of my life.
I went on to deploy to Iraq and Afghanistan. Between deployments, I worked at the Wounded Warrior Battalion in San Diego, supporting Marines as they rebuilt their lives. What I did not understand was how deeply I was absorbing their grief and losses.
That became clearer when I later deployed to Afghanistan during one of the deadliest periods of the war for Marines. I purposefully stopped counting the flag-draped coffins as they were loaded onto planes to return home, swallowing my grief so I could return to the mission.
I became paralyzed watching young Marines go outside the base, thinking about their families and whether they would see them again. I began hallucinating that wounded Marines I cared for were walking toward me in the war zone. I now recognize that, alongside my own PTSD, I was carrying secondary PTSD from caring for wounded Marines.
With every loss, I swallowed what I felt just to keep functioning. I kept moving forward, until everything I buried became impossible to ignore.
I did not recognize what was happening until five years after returning home. I sought help. Therapy helped me feel less alone, but my symptoms continued to affect my life and relationships.
My experience is not unique. 870,000 veterans receiving VA health care were diagnosed with PTSD in 2024. Since 9/11, nearly 150,000 veterans have died by suicide. Many continue searching for relief after available treatments have failed.
That is why veterans are cautiously hopeful about psychedelic treatments.
Studies of psilocybin for treatment-resistant depression show significant reductions in depressive symptoms, with up to one-third of patients achieving remission in some trials. Research involving veterans with PTSD found that 75% were in remission one month after psilocybin treatment.
I followed the research before pursuing psilocybin treatment myself. During that experience, I was finally able to access the grief I spent decades burying. It did not erase what happened or the memories of the Marines I lost. It changed my relationship with those memories. They no longer controlled my life.
I reconnected to the self I had lost and was able to feel joy and love again.
Psychedelic medicines are not a cure-all. But veterans pursuing them are not looking for shortcuts. Many have spent years doing everything the medical system asked while continuing to search for relief.
Our government is beginning to recognize the potential of new approaches.
This year, President Trump signed an executive order to accelerate research and reduce barriers to psychedelic treatments for serious mental illness. VA is conducting clinical trials of MDMA for PTSD and psilocybin for depression. In July, FDA finalized guidance for clinical trials involving psychedelic drugs.
If these treatments receive FDA approval, the healthcare system must be ready to deliver them responsibly — through DEA action, clear safeguards, and VA facilities prepared to provide care.
Our country asks a great deal of those who serve. If evidence demonstrates that these treatments are safe and effective, veterans should not wait years longer because Washington failed to prepare for success.
Juliana Mercer is a Marine Corps veteran and executive director of Healing Breakthrough. A version of this column was published in Stars and Stripes.
Black Press
OP-ED: Haiti TPS: Have We Lost Sense of Humanity?
BLACKPRESSUSA NEWSWIRE — The treatment of more than 300,000 Haitians living and working in the United States under Temporary Protected Status (TPS) presents such a moment. The Senate should pass S.4814, legislation that would extend TPS for Haitians for three years. The Senate’s Republican members hold a critical key to whether Congress will act before the midterm elections.

There are moments when a nation must decide, not simply what it has the legal power to do, but what its sense of humanity requires it to do.
The treatment of more than 300,000 Haitians living and working in the United States under Temporary Protected Status (TPS) presents such a moment. The Senate should pass S.4814, legislation that would extend TPS for Haitians for three years. The Senate’s Republican members hold a critical key to whether Congress will act before the midterm elections.
There are several reasons that the Haitian TPS question is a genuine crisis. First and foremost, Haiti is dangerously unsafe, and the justification for TPS could hardly be clearer.
Haiti continues to experience extraordinary violence and instability. United Nations and human-rights organizations report killings, kidnappings, sexual violence, displacement and widespread abuses by armed gangs. Millions of Haitians face acute humanitarian needs.[1]
Most tellingly, the U.S. Department of State warns Americans: “Do Not Travel” to Haiti, citing kidnapping, crime, terrorism, civil unrest and limited health care.[2]
That warning raises an unavoidable question: If Haiti is too dangerous for Americans to travel there, how can it be considered safe to compel more than 300,000 Haitians to return?
Congress created TPS precisely for circumstances in which armed conflict or extraordinary conditions make safe return impossible or inappropriate.[3] The documented conditions in Haiti meet that humanitarian standard many times over.
Let’s also clear up another misimpression. The Supreme Court in its June 25, 2026 decision in Mullen v. Doe did not order TPS to end and it did not order Haitians to be deported.
Rather, the Court ruled that the Department of Homeland Security (DHS) had the primary responsibility to decide when to grant TPS and that its decisions were not, in most instances, judicially reviewable.[4]
The decision therefore permitted the Administration’s termination of Haitian TPS to proceed, but the humanitarian question of whether it should proceed remains with the political branches. In other words, Congress retains its legislative authority to act. S.4814 is Congress exercising that authority.
For Haitians living under the threat of deportation, this is not an abstract legal dispute. The human cost is becoming painfully real.
Consider Pierre Damas Bel, a 20-year-old Haitian college student with a promising future, who lived in Springfield, Ohio. After losing his immigration protection, he was placed on an ICE ankle monitor. His family has described the profound psychological distress he experienced.
Bel subsequently died after stopping his car and walking into traffic on a crowded Ohio highway. His family believes it was suicide Authorities are investigating, and it would be irresponsible to claim that immigration policy alone caused his death. But his tragic story illustrates the human consequences of creating fear and uncertainty for people who have lived, studied and worked lawfully in this country and have no immediate expectation of returning home safely.[5]
There also is another compelling reason for Congress to act: Haitian TPS holders are caring for Americans.
Approximately 21,000 Haitian TPS holders work as caregivers and nursing assistants, serving an estimated 77,000 patients nationwide.[6] They care for seniors in nursing homes, assist people with disabilities and provide home care that allows vulnerable Americans to remain in their communities.
When experienced Haitian caregivers lose their legal ability to work, families must scramble to find replacements, nursing facilities face staffing shortages, and vulnerable people can lose caregivers they have trusted for years.
At a time when America already faces a serious shortage of direct-care workers, deporting thousands of experienced Haitian caregivers is not merely inhumane, it’s self-defeating and contrary to our nation’s own healthcare needs.[7]
The mass deportation of Haitians also presents a troubling humanitarian double standard that Congress should confront.
The Trump Administration has made a special effort to admit White South African Afrikaners as refugees, citing racial persecution and violence — a dubious claim at best. At the same time, it is stripping protection from Haitians whose country is experiencing catastrophic violence, death and insecurity.
The State Department currently rates South Africa for travel recommendations at Level 2—“Exercise Increased Caution.” Haiti is at Level 4—“Do Not Travel.”[8]
Every person facing genuine persecution deserves humanitarian consideration and protection, but humanitarian standards should be applied consistently. If America can recognize humanitarian danger facing White South Africans, surely it can recognize the documented and extraordinary danger confronting Black Haitians.
The disparity deserves congressional scrutiny—not because one group should receive less protection, but because humanitarian protection should not depend upon race or political convenience.
Finally, the Haitian TPS question should not be reduced to a partisan argument.
Republican Ohio Governor Mike DeWine has criticized the Administration’s approach to Haitian immigrants and warned of the consequences of ending TPS. Democratic Maryland Governor Wes Moore has likewise expressed opposition to returning Haitians to dangerous conditions.[9]
These governors understand that immigrants are not merely immigration cases. They are workers, taxpayers, caregivers, parents, students, neighbors and members of their communities.
The House of Representatives has already taken action and passed a bill to restore Haitian TPS.
The Senate’s Haitian TPS bill (S.4814) offers a measured response: three additional years of protection while Haiti confronts its extraordinary crisis. It is not amnesty! It does not grant citizenship or permanent residence. It does not repeal America’s immigration laws. It does, however, provide important and humane temporary protection while conditions make return to Haiti unsafe.
Our history tells us what happens when government treats human beings with hostility and indifference, and regards humanitarian appeals as inconveniences to be overcome.
America can and must do better.
The Senate now has an opportunity to demonstrate that America’s humanitarian principles apply consistently—to Black immigrants as well as everyone else. Republican senators hold a critical key to bipartisan action. Before the midterm elections, they should join Democrats in responding to this humanitarian imperative.
Our nation’s sense of humanity demands it.
Wade Henderson, Esq. is a civil and human rights attorney in Washington, DC. He serves as a Senior Advisor to the Haitian Bridge Alliance.
Endnotes
- United Nations Integrated Office in Haiti (BINUH), Human Rights Reports; Human Rights Watch, World Report 2026: Haiti.
- U.S. Department of State, Haiti Travel Advisory, Level 4—“Do Not Travel.”
- 8 U.S.C. §1254a(b)(1).
- Mullin v. Doe / Trump v. Miot, U.S. Supreme Court, June 25, 2026.
- Washington Post, “College student steps into traffic, is killed after losing immigration status,” Sept. 1, 2026; ABC News, Sept. 1, 2026. Authorities continue to investigate Bel’s death.
- Reuters, “US families, healthcare providers under strain after Trump crackdown on Haitian immigrants,” Aug. 19, 2026.
- Id.; see also reporting by LeadingAge concerning the impact of ending Haitian TPS on senior and disability care.
- U.S. Department of State, Haiti Travel Advisory; South Africa Travel Advisory.
- Reporting on statements by Ohio Gov. Mike DeWine and Maryland Gov. Wes Moore concerning Haitian TPS.
Black History
COMMENTARY: Battling Black Voter Distrust
HOUSTON DEFENDER — Black voters have long been a reliable base for the Democratic Party, but political strategists and voters indicate that years of inconsistent engagement and unfulfilled expectations have created a trust gap.

Black voters have been among the Democratic Party’s most dependable supporters for generations. But loyalty and trust are not the same thing.
With less than a month to go before the midterm elections, Black voters and political strategists say years of inconsistent engagement and unmet expectations have left some voters questioning whether the party has earned their continued support. The challenge now is bigger than winning votes. It’s convincing distrustful voters that staying politically engaged is worth it.

Communications strategist Ashley Etienne argues that Democrats have spent years taking one of their most reliable voting blocs for granted, creating a widening trust gap that threatens the party’s long-term prospects in Texas and nationally.
“Trust is the currency of persuasion,” she said. “We’re seeing distrust at an all-time high, especially with Black voters … distrust of the media, institutions, the Democratic Party, self-agreement. Campaigns don’t lose because they fail to talk to voters. They lose because they fail to listen.”
Etienne, who served as a senior adviser to Presidents Barack Obama and Joe Biden and communications director for Vice President Kamala Harris, said repairing that relationship requires something considerably more difficult than another campaign advertisement. It requires listening.
Black support remains strong, but not absolute
Recent polling suggests Democrats continue to hold a substantial advantage among Black voters heading into November, but that support isn’t universal.
A July 2026 Pew Research Center survey found 68% of Black registered voters said they would support the Democratic candidate for U.S. House in their district, compared with 8% who favored the Republican. Another 25% said they were either unsure or would support another candidate.

That uncertainty follows some erosion in Democratic support among Black voters in the 2024 presidential election. A Pew analysis of validated voters found 83% of Black voters supported Kamala Harris in 2024, compared with 92% who supported Joe Biden in 2020.
Pew found that shift was driven less by individual voters switching from one party to another than by differences in who turned out to vote.
The findings don’t suggest Black voters have abandoned Democrats. They do raise questions about whether longstanding party loyalty is enough to guarantee participation.
“We’ve been making that same argument decade after decade,” Etienne said. “Those are becoming less persuasive arguments.”
Why is trust disappearing?
The distrust isn’t necessarily about one candidate or one election. For some Black voters, frustration comes from feeling heavily courted during election season without seeing enough progress afterward on the issues affecting their daily lives.
Housing costs remain a concern. So do education, economic opportunity, neighborhood investment, and the cost of everyday necessities.
That creates a difficult dynamic for campaigns: Asking voters to participate in a political system that some believe has not delivered enough for them.
It also raises a separate question. What happens when frustration with political parties becomes disengagement from the political process altogether?
What happens when voters stay home?
The answer can become particularly consequential in local elections, where races can be decided by hundreds of votes rather than thousands.
Harris County Democratic Party Chair Traci Gibson has pointed to several 2024 judicial races decided by narrow margins. District judge candidate Elaine Palmer lost by 304 votes, while Jeralynn Manor lost by 647 votes.
Gibson also warned about voters who begin Harris County’s lengthy ballot but don’t finish it.
“If you go into these polls and you vote for the first five people and then you leave, that’s how we get Elaine Palmer losing by about 300 votes,” Gibson said.
The larger issue extends beyond any candidate or political party. Judges are elected. School boards make decisions affecting students and families. City and county officials determine how public dollars are spent. State lawmakers decide which bills become state law.
Those decisions are made regardless of how many eligible voters participate.
“We have to have strategies, we have to have plans, we have to have a mechanism in place for people to feel they are heard.”
Karla West
For voters distrustful of political parties or government institutions, political participation also doesn’t have to mean unquestioning loyalty to either party.
Voters can research candidates individually, compare their positions, attend or watch candidate forums and examine an incumbent’s record against previous campaign promises. They can also learn what the often-overlooked offices farther down the ballot actually control.
In that sense, distrust can become a reason for greater scrutiny rather than disengagement.
Candidates have work to do, too
Responsibility for rebuilding participation doesn’t fall solely on voters.
At a recent Third Ward town hall hosted by state Rep. Jolanda “Jo” Jones, Harris County Precinct 7 Constable James “Smokie” Phillips and Houston Black American Democrats, voters and political strategists called for more sustained campaign engagement.
“Investment drives outcomes. If you don’t invest in it, it doesn’t work,” Etienne said.
She argued that campaigns spend heavily on polling, consultants and advertising while directing too little money toward Black-led political infrastructure and organizations with established relationships in Black communities.
Shamier Bouie, chair of Houston Black American Democrats, said organizing cannot begin a few months before Election Day.
“It’s all about year-round organizing, and increased investment in Black voter outreach … more funding for Black-led organizations that have relationships, infrastructure, and experience in effectively engaging Black communities,” Bouie said.
The question of investment also surfaced in July when Democratic U.S. Senate candidate James Talarico pledged $25 million toward Black voter outreach. Some voters wanted specifics about where and how that money would be spent.
“We still need our kids, we still need our schools equitably funded,” said Augie Cahee, vice president of marketing web delivery at JPMorgan Chase & Co. “So, we want to know what you’re going to do with the money. Don’t stand up and tell me $25 million and you don’t have a plan.”
The exchange illustrated the larger trust problem: Voters aren’t simply asking candidates to talk to them. They want to know what happens after the conversation.
From distrust to accountability
Karla West, a precinct chair for downtown’s Precinct 16, said responsibility ultimately belongs on both sides.
“We fell asleep at the wheel,” West said of voter turnout.
But she also challenged political leaders.
“The Democratic Party did not say what they would do for you,” West said. “We haven’t heard a plan for years. I’m sick of it. We have to have strategies, we have to have plans, we have to have a mechanism in place for people to feel they are heard.”
Defender Reporter Tannistha Sinha contributed to this report.
Based on reporting by Houston Defender.


CalAIM Helped Alfred Flores Rebuild His Life. Why Can’t More Californians Access Its Benefits?

Kia Seltos: Advanced Safety & Tech Features Explained #shorts

How Inglewood’s Homeless Seniors Are Finding Relief Through Housing and Trauma-Informed Care

Carmen Meeks Turns Teachers’ Lessons Into a Legacy | 2026 Education Salute

Street Medicine Brings Care to Unhoused Angelenos — But Housing Remains the Missing Prescription

2 Crucial Bolt EV Interior Details You MUST Inspect! #shorts

California Becomes First State to Require Slavery-Ties Disclosure 📱

California Becomes First State to Require Slavery-Ties Disclosure

OP-ED: Washington Has a Chance to Save Veterans’ Lives

OP-ED: Haiti TPS: Have We Lost Sense of Humanity?

Women Learned Their Jail Strip Searches Were Recorded. Their Outrage Changed the Law

Latest Massacre in Haiti Reveals Cruelty U.S. Deportations

Black Americans Have Doubts About the U.S. Food System

When Praises Go Up: SUGC Nominated for Prestigious Stellar Award.

Booked and Unbound: The Legacy of Black Women’s Literary Circles

U.S. Sole Nation to Oppose U.N. Resolution Correcting Africa’s Size on World Maps

Prostate Cancer is Twice as Likely to Kill Black Men. Talking to Your Doctor Could Help Save Your Life

Outnumbered: Elbert Cox’s Equation for Greatness

COMMENTARY: Big Mama Said ‘Don’t Let Grief Break the Bank’

U.S. Open Influencers Spark Backlash over Ring Lights, Filming as Gauff and Osaka Speak Out
Kia Seltos: Advanced Safety & Tech Features Explained #shorts
Carmen Meeks Turns Teachers’ Lessons Into a Legacy | 2026 Education Salute
2 Crucial Bolt EV Interior Details You MUST Inspect! #shorts
California Becomes First State to Require Slavery-Ties Disclosure 📱
California Becomes First State to Require Slavery-Ties Disclosure

Unpacking “Playing the Game”: Race, Brilliance & Sports Secrets! #shorts

Xantavious: No Limits on What I Can Achieve #shorts

“I’m Just As Good As You”: Lewis Neal Retires After 35 Years With Bakersfield City Schools

Beyond Beasts: Black Athletes’ Brilliance & Divine Intelligence #shorts

From Loss to Legacy: Forever Remain Motivated #shorts
-

 Black History1 week ago
Passing for White, Fighting for Black America: The Courage of Walter White
-

 Black History1 week ago
The Youngest American Killed in the Vietnam War
-

 Black History4 days ago
Remembering Chauncey Bailey as Student Journalists Face Threats to Truth-Telling
-

 Black Press1 week ago
Mayor Lee Announces $1 Million Kaiser Permanente Grant for Pilot Program to Address Homelessness, Clean Up Public Spaces throughout Oakland
-

 Black Press1 week ago
OP-ED: How Head Start Also Helps Parents
-

 Art1 week ago
Peter Magubane: a Camera Against Apartheid
