
Health
Early stuttering common, not tied to development issues


[REUTERS]
More than one in 10 children had a stutter by age four in a new Australian study, but those kids scored just as high or higher than their peers on assessments of language, thinking skills and temperament.
“Stuttering onset is relatively common but parents can be reassured that developmental stuttering is not associated with poorer outcome in the preschool years at least,” Sheena Reilly, the study’s lead author from the Murdoch Childrens Research Institute in Parkville, said.
The researchers said the frequency of stuttering among their preschoolers – about 11 percent – was higher than in previous studies, perhaps because they started following the children very early in life.










Black Press
CalAIM Helped Alfred Flores Rebuild His Life. Why Can’t More Californians Access Its Benefits?
BAKERSFIELD NEWS OBSERVER — “Under CalAIM, there has been this incredible ability to pay for certain things that are helpful to anyone experiencing homelessness,” said Margot Kushel, Professor of Medicine, UCSF Director of UCSF Benioff Homelessness and Housing Initiative. “We can pay for things like street medicine. We can pay for enhanced case management, housing tenancy support services to keep people in their housing, and things like first and last month’s rent to help people.”

CalAIM offers housing and health care support through Medi-Cal, but fragmented health-plan rules, administrative barriers and limited awareness can make those benefits difficult for vulnerable Californians to access.
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship.
By Marion Apio | California Local News Fellow
California’s largest Medi-Cal transformation—California Advancing and Innovating Medi-Cal, or CalAIM—was designed to connect residents experiencing homelessness, trauma, and chronic illness directly to health care and social services. The statewide initiative allows healthcare providers to bill Medi-Cal for intensive, field-based care coordination, bringing doctors, social workers, and housing navigators directly to unsheltered residents where they live.
Yet despite CalAIM’s ambitious promise to fund care outside clinic walls, health care providers say many unhoused Angelenos still face steep barriers to accessing these services. Health plans have not always been aligned on which services to offer, creating a patchwork of coverage across the state. For patients, those differences can mean delays in approvals, changes in available services or additional paperwork before care or housing assistance can move forward.
“Under CalAIM, there has been this incredible ability to pay for certain things that are helpful to anyone experiencing homelessness,” said Margot Kushel, Professor of Medicine, UCSF Director of UCSF Benioff Homelessness and Housing Initiative. “We can pay for things like street medicine. We can pay for enhanced case management, housing tenancy support services to keep people in their housing, and things like first and last month’s rent to help people.”
“Pathways to housing are highly effective, she added, “but we need more of them. The problem is not so much that it doesn’t work for the people it’s serving; it’s that it’s under-resourced for the people it’s serving, and most people don’t get it.”
Across Los Angeles County, community organizations and street medicine teams report spending significant hours navigating complex enrollment portals and billing hurdles that delay care for residents in critical need.
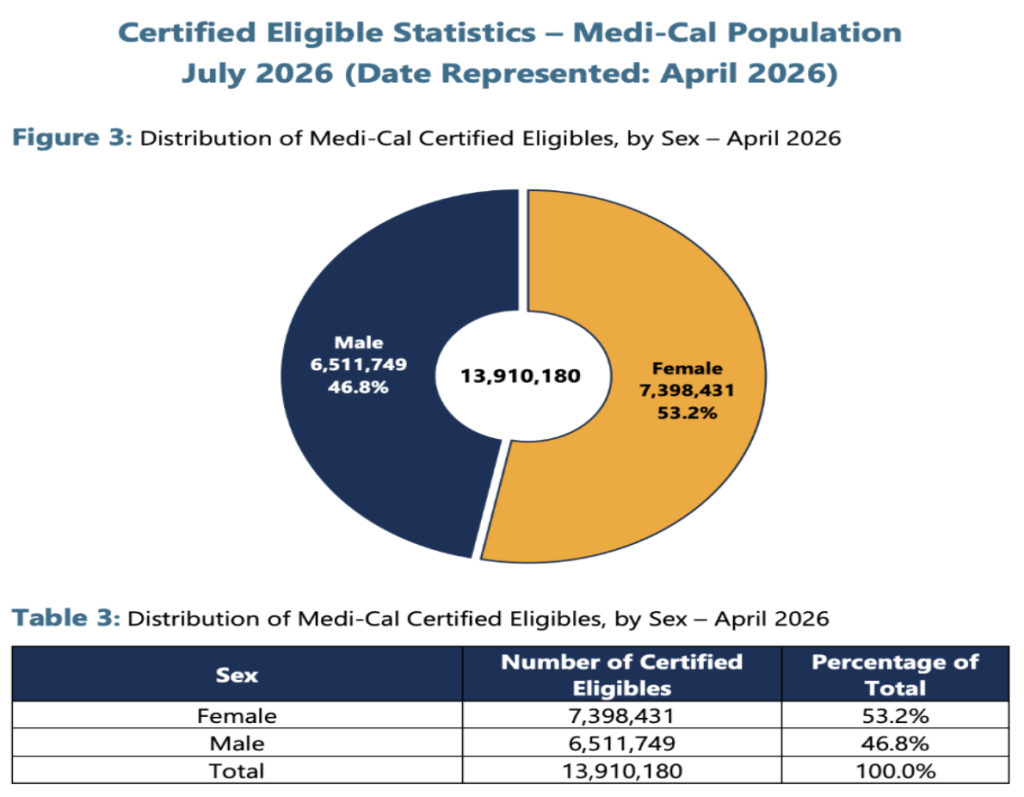
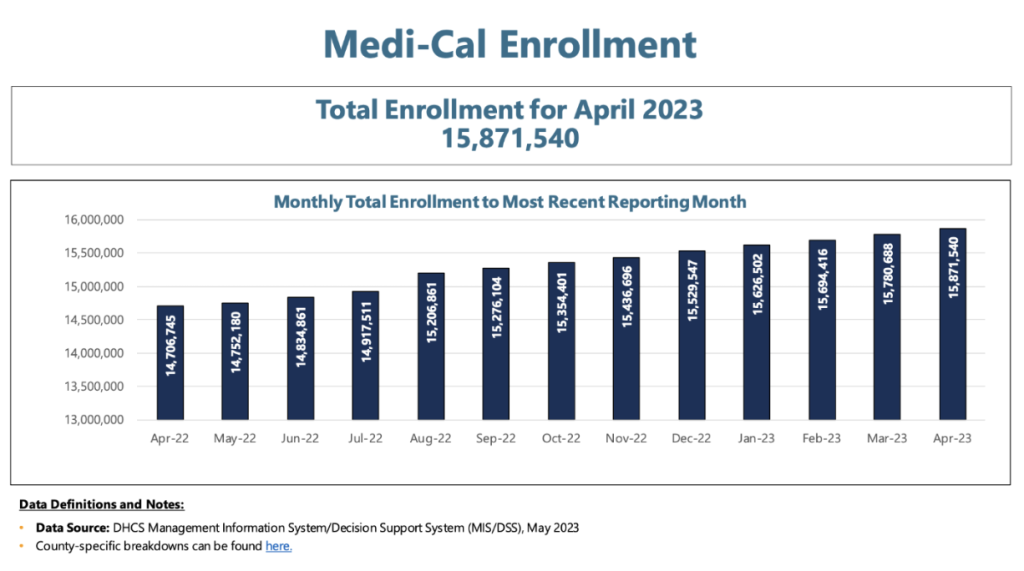
More than four years after California launched CalAIM to use Medi-Cal funding for nonmedical needs such as housing, food and case management, overall Medi-Cal enrollment has declined from about 15 million in 2023 to 13,910,180 in April 2026, according to the California Department of Health Care Services. CalAIM is not a separate insurance program and does not have its own enrollment or withdrawal process; people enroll in Medi-Cal and may qualify for CalAIM services based on their needs.
For 53-year-old Alfred Flores, connecting with a CalAIM-funded street medicine team along the Los Angeles River proved transformative.
Flores was only 17 when he first entered California’s prison system as an adult.
Raised around family members involved in gang life and without financial resources for a private legal defense, the young Flores cycled through juvenile halls and state prisons, including the California Institution for Men in Chino and a correctional facility in Delano.
“I was tried as an adult and we didn’t have any lawyers or nothing,” Flores said. “So, yeah, I was misjudged, you know. But it is what it is.”
Decades after his release, the consequences of incarceration lingered. Diagnosed with severe post-traumatic stress disorder, Flores struggled to navigate crowded public spaces and complex social service systems. Unhoused and contending with uncontrolled diabetes, his health rapidly deteriorated.
Flores’ path changed when he met Artie Vasquez, a community health worker and case manager with St. John’s Community Health. Vasquez helped Flores navigate and access medical care through case management services provided under CalAIM’s Enhanced Care Management benefit — and, just as importantly, helped him secure an apartment in Inglewood using Medi-Cal dollars.
Enhanced Care Management (ECM) — a Medi-Cal benefit that provides intensive, individualized care coordination for members with complex needs — pairs members with a care manager who coordinates physical, behavioral and social services, while Community Supports address needs such as housing instability, nutrition and chronic-condition management.

“I can go in and out of my house. I can shower whenever I want. Use the restroom whenever I want. It’s my house, you know,” Flores said.
Artie Vasquez, who overcame similar life challenges before becoming a case manager, said the program provides the scaffolding needed for individuals leaving incarceration to successfully transition back into society.
Medi-Cal covers close to 14 million residents statewide. In Los Angeles County, where over 70,000 people experience homelessness on any given night, connecting high-need populations to social safety nets remains an operational challenge.
CalAIM addresses these challenges through Community Supports, or non-medical interventions, such as move-in security deposits, housing navigation, and modifications to make housing accessible.
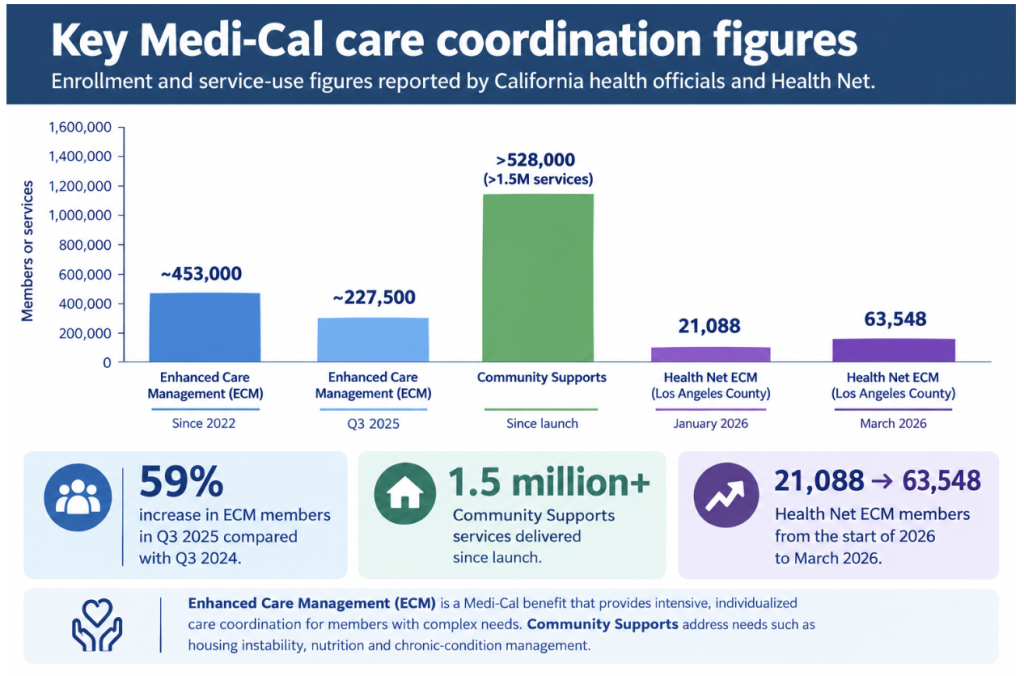
For frontline clinics, the growth in such services represents a massive shift in how care is delivered.
Christina Guevara, an Enhanced Care Management program manager at St. John’s Community Health has watched this safety-net infrastructure expand over six years.
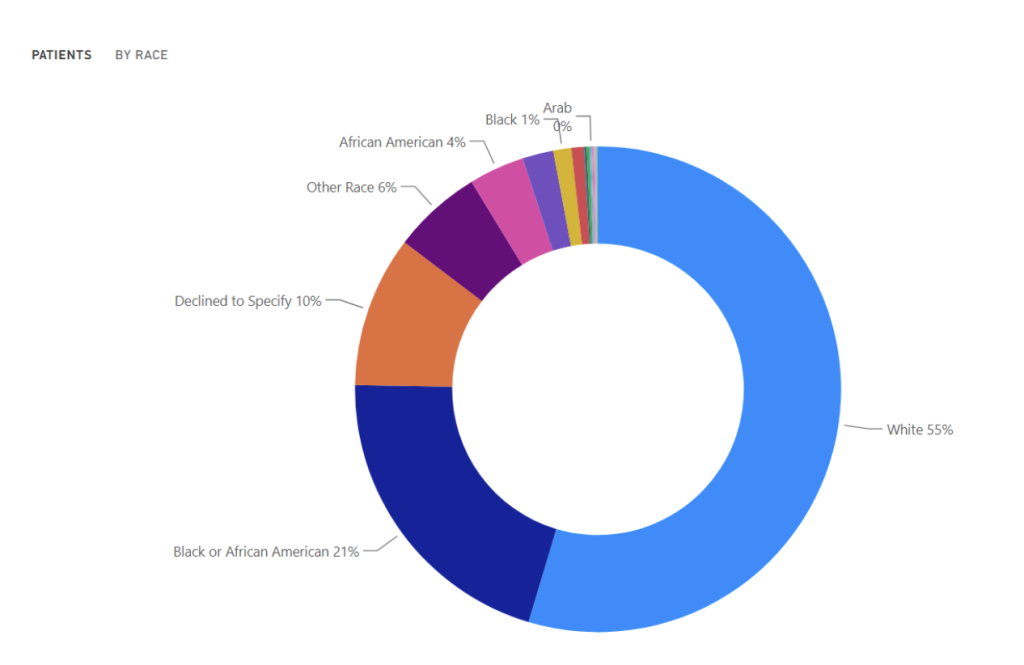
In just the past three years, St. John’s CalAIM caseload has surged from under 1,000 patients to nearly 1,600, serving a community that is roughly 55% Latinos and White as well as 26% Black, according to Monica Cotom, director of CalAIM at St. John’s Community Health.
Guevara noted that language barriers, low health literacy, and a lack of support systems frequently cause low-income patients to drop out of care. She said that is especially true for older patients who may struggle to navigate complex medical instructions or question a doctor’s diagnosis.
In one instance, St. John’s case managers worked with an unhoused domestic violence survivor living in a shelter who avoided medical visits out of fear of being located by an abuser. Through biweekly phone calls, virtual support groups, and accompanied clinic visits, case managers helped the survivor secure permanent housing and reduce his hemoglobin A1C level from a dangerous 14% down to 7% over an 18-month period.
Yet, administrative breakdowns regularly interrupt patient care.
“The health plans have never been quite aligned for this program across the board, and so that’s been the barrier,” said Cotom. “We have to fluctuate with whatever the health plans need, and so that makes it hard.”
Because each Medi-Cal managed care plan operates with its own documentation requirements, billing systems, and approval rules, caseworkers must constantly adapt to conflicting administrative processes. For unhoused patients, these hurdles translate directly into real-world delays. For unhoused clients, bureaucratic errors can pause housing placements for months.
In Inglewood, city officials acknowledge that awareness remains a barrier.
Roberto Chavez, HUD programs manager for the City of Inglewood, called CalAIM an “untapped resource,” and noted that municipal governments currently lack public education campaigns to connect eligible residents with the state program.
“Not too many people are aware of that,” Chavez said. “Again, that requires some education of the residents and people experiencing homelessness, as well as any staff that’s in charge of identifying resources.”
When asked what the city is doing to publicize CalAIM to unhoused residents, Chavez said the city relies on partner non-profits rather than municipal outreach.
“Nothing at the current moment,” Chavez said. “But we direct folks to the St. Margaret’s Center, and they make folks aware of the CalAIM program, as well as the South Bay Cities Council of Governments.”
Addressing why local agencies struggle to roll out CalAIM seamlessly, Kushel called it a nearly impossible task.
“When you’re frantically trying to plug up holes from 50 years of failed policies at every level of government in a wildly unequal country where there’s rampant income inequality … it’s also really an impossible task,” Kushel said, adding that local authorities are “trying to put fingers into sort of a leaking bucket, and it’s very hard to do that.”

Ashley Watson was offered CalAIM services in June 2025 while living in her car in Los Angeles. Working with Stephanie Ortiz, a case manager, Watson secured several jobs to raise her monthly rental budget from $1,200 to $2,000. When bad credit led to apartment rental rejections, Ortiz assisted in securing a guarantor.
However, during the application process, an administrative error caused Watson’s Medi-Cal coverage to terminate unexpectedly. It took nearly a month of staff effort to restore her coverage before security deposit and move-in funding could be released. Watson moved into her apartment in November 2025 and officially graduated from the program in June 2026.
Mary Vargas, Community Supports program manager at St. John’s, said administrative gaps leave the most vulnerable clients behind.
“A lot of people don’t understand why and feel powerless in their own care,” Vargas said. “If you’re powerless, have a chronic condition, and are alone with no support, your health significantly declines.”
Guevara reported that rising fears around immigration status and potential scams have led members to decline home visits or ignore phone calls from case managers. To support clients facing these anxieties, St. John’s transitioned many in-person check-ins to virtual appointments.
DHCS acknowledged that some immigrant families are experiencing fear about data-sharing with federal agencies that might use the information in enforcement actions. The department said it does not track whether people decline CalAIM services because of those concerns, but encouraged eligible Medi-Cal members to maintain their coverage and continue seeking care.

Vasquez noted that individuals released from state prisons face delays of 30 to 90 days before their active Medi-Cal status is reinstated.
Those delays force clinics to rely on sliding-scale fees based on income –which many newly released participants do not have –while unhoused individuals without physical addresses often rely on family members’ addresses to keep their mail delivered and avoid losing coverage.
But for those who get past the hurdles and receive services, the results can be life changing.
Flores is now enrolled in online business and culinary arts classes through Coastline College, working toward his long-term goal of financial independence.
“Before, I didn’t know how to go about things, but now with my medication, my doctors, and my case manager who always calls to see if I’m doing okay, it has helped me a lot—and I can trust the system,” Flores said.
Black Press
How Inglewood’s Homeless Seniors Are Finding Relief Through Housing and Trauma-Informed Care
BAKERSFIELD NEWS OBSERVER — For people like Gilbert Ramirez, the dangers of living on the street compound with age. Chronic illnesses become harder to manage, mobility declines and minor health problems can quickly escalate into medical emergencies without a stable place to recover or store medications. Increasingly, this vulnerable population includes seniors falling into homelessness for the first time after a lifetime of low-wage, physically demanding work.
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship.
For 70-year-old Gilbert Ramirez, the intersection of medical care and supportive housing proved lifesaving.
First sent to prison at 25, Ramirez spent decades cycling through nine separate sentences and three decades of parole supervision before finally completing parole seven years ago.
“I’ve been told what to do, man, for all my adult life,” Ramirez said. “I had nine turns on one number, and finally they gave my life back. So now I’m a free citizen.”
While incarcerated, he and his wife separated. After returning to society, he lost his daughter to cancer, was shot, and was left partially paralyzed and unhoused.
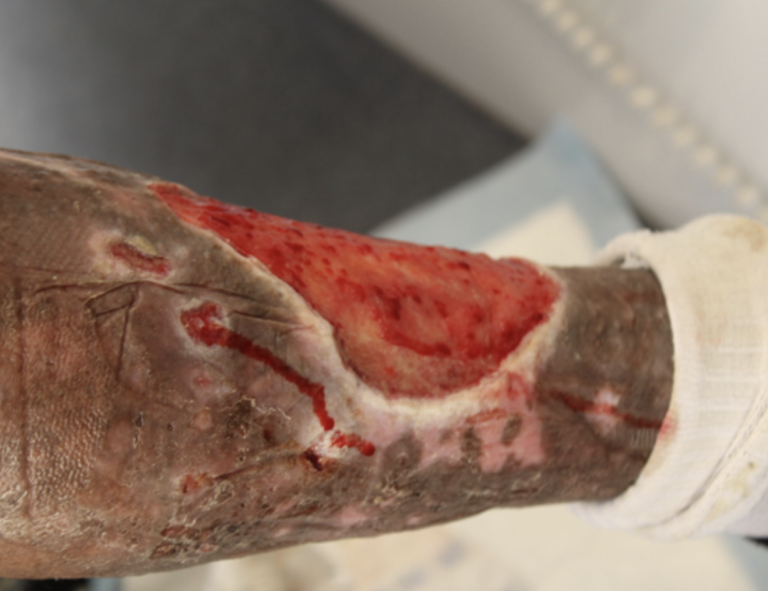
Surviving on the street, Ramirez fell into a heavy fentanyl addiction. For seven years, severe, open wounds flared on both of his legs—wounds he had no way of healing while living unhoused.
As the infections worsened, his weight plummeted to 95 pounds.
Compounding challenges for seniors who are unhoused
For people like Ramirez, the dangers of living on the street compound with age. Chronic illnesses become harder to manage, mobility declines and minor health problems can quickly escalate into medical emergencies without a stable place to recover or store medications. Increasingly, this vulnerable population includes seniors falling into homelessness for the first time after a lifetime of low-wage, physically demanding work.
“We have a large proportion of seniors experiencing homelessness—about 43 percent who had never been homeless before after the age of 50,” said Margot Kushel, professor of medicine, UCSFDirector of UCSF Benioff Homelessness and Housing Initiative
Eight months ago, outreach workers with People Assisting The Homeless—a nonprofit housing and social services agency—moved Ramirez into the Los Angeles Inn in Inglewood. They did so under an L.A. County-led initiative that brings unsheltered residents indoors by placing them inmotels converted into interim housing. It also connects clients with wraparound healthcare and case management.The effort primarily receives funding through L.A. County’s Measure A sales tax, which aims to create a direct pipeline from street encampments to permanent housing.
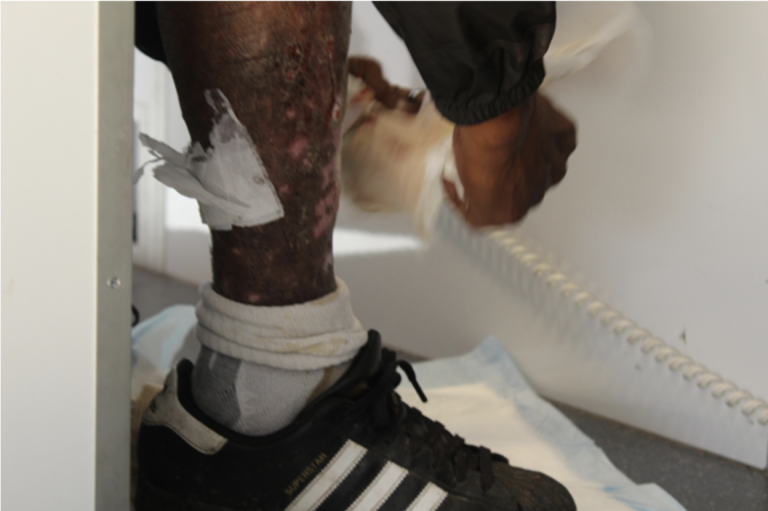
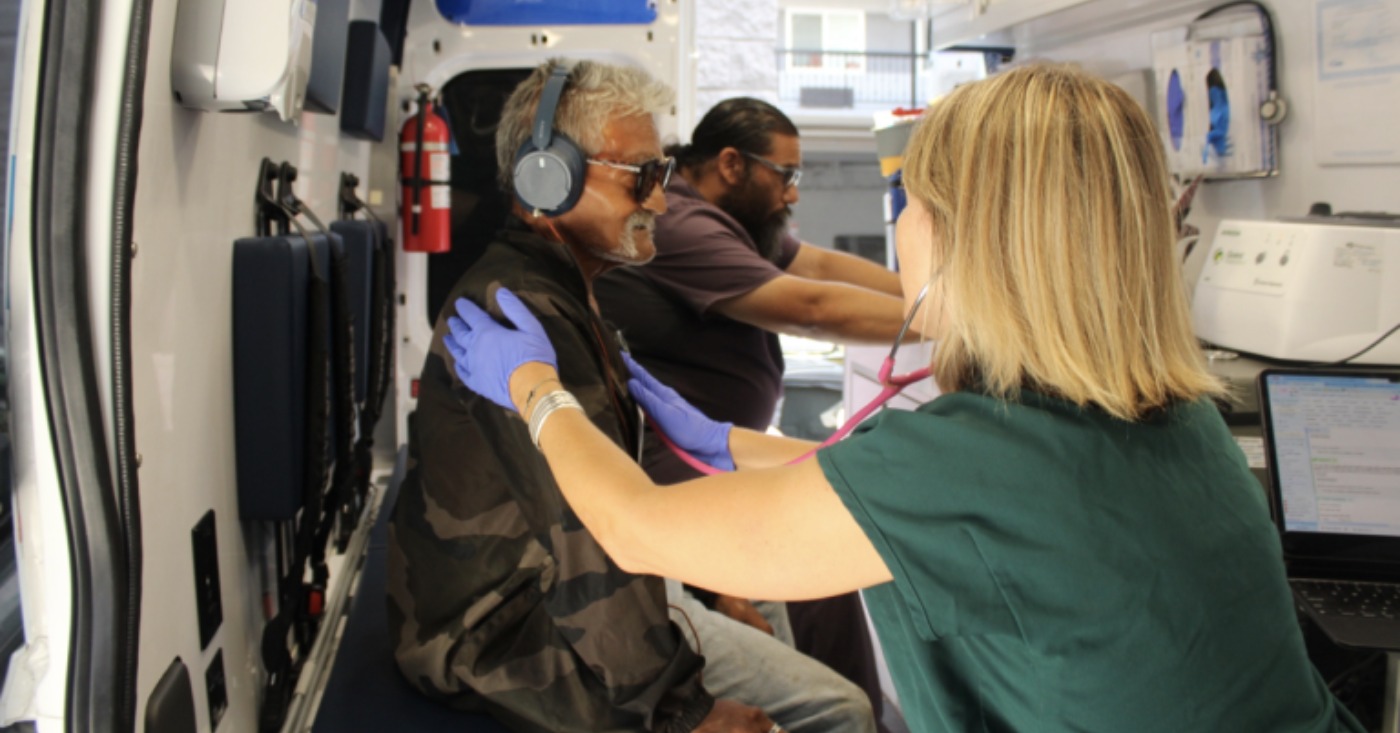
By the time Ramirez connected with Carrie Kowalski last November, a senior physician assistant with Venice Family Clinic, the wounds on both of his legs were deep, painful, and itchy. Kowalski cleaned and wrapped the wounds and provided Ramirez with naloxone nasal spray—an emergency overdose reversal drug – along with fentanyl test strips and buprenorphine starter supplies, a medication used to treat opioid addiction.
“It’s good, I ain’t now underweight,” Ramirez said about the services he receives under Pathway Home. “They offer me medicine. They come and, you know, give you everything. Whatever I need—a doctor, food, a bed, water, and everything I never had before.”
From August 2023 to August 5, 2026, Pathway Homehad moved 2,361 people into interim housing, while 892 had moved into permanent housing, according to Los Angeles County. The county said the biggest barrier to moving people from interim to permanent housing is the shortage of affordable permanent homes.
Pathway Home’s mission is to reach encampments throughout L.A. County and link people to permanent housing, said Courtney Reed, associate director at PATH.
“We operate in what we call a trauma-informed care model,” Reed said.

The Los Angeles County’s Pathway Home budget for fiscal year 2026-27 is $59.5 million. The funding includes $24.4 million from Measure A, $19.8 million in Measure H carryover, $13.8 million in state Encampment Resolution Fund carryover and $1.5 million from the county Department of Mental Health, according to information provided by the county in an email. In April 2024, the county also received a $51 million grant from the state of California to expand the Pathway Home program.
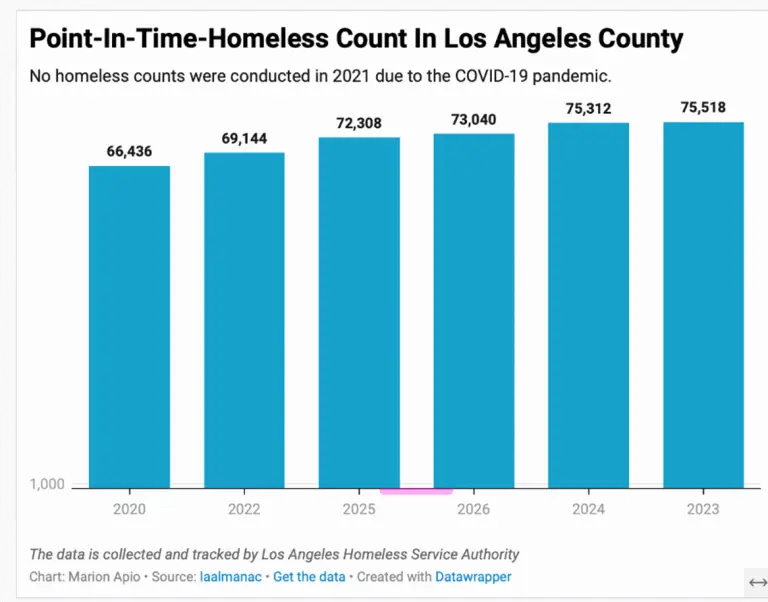
Countywide, the number of unhoused adults ages 55 and older rose nearly 5 percent, from 18,212 in 2025 to 19,104 in 2026, accounting for about 26% of the county’s 73,040 unhoused residents. Black residents continue to be disproportionately represented among the people experiencing homelessness, accounting for 21,822 people of the unhoused population within the Los Angeles Continuum of Care, according to the 2026 Greater Los Angeles Homeless Count.
A shortage of affordable housing has limited options for the unhoused in Inglewood
In Inglewood, Pathway Home teams have moved 54 people into temporary housing in motels, according to the mayor’s office. While experts call this placement critical for vulnerable seniors, city officials clarified Inglewood is strictly a logistical partner.
“We have no funding obligation, Pathway Home Initiative is funded by the County of Los Angeles,” said Roberto Chavez, Inglewood’s HUD programs manager. “The city is a partner.”
However, transitioning people into permanent housing has also become more difficult in Inglewood, where the city’s housing voucher program is frozen under a “designated shortfall” from the U.S. Department of Housing and Urban Development because federal funding failed to match local rent increases.
“The housing authority has spent its annual allocation, and HUD is monitoring our finances,” Chavez said. “The result is we’re not able to issue more vouchers to families to get housing.”
While homelessness continues to trend downward in Inglewood—where the unsheltered population dropped from a peak of 751 individuals in 2022 to 290 in 2026—countywide data masks a growing crisis among older and Black residents.
Challenges for seniors who are unhoused
By the time outreach workers connected with Jacqueline Thomas last November, the 67-year-old was hauling an oxygen tank across La Brea Avenue while managing a heart condition, chronic obstructive pulmonary disease, diabetes, and a daily regimen of 13 prescription pills—all while living out of her car.

A 1976 graduate of Inglewood High School, Thomas’s life unraveled a decade ago after she lost her job. Faced with fixed income limits and rising housing costs across L.A. County, strain over rent money eventually frayed family ties, leading her to choose the streets over an unstable living situation.
For 10 years, Thomas parked her car outside businesses along La Brea Avenue to sleep. She let other unhoused neighbors stay inside with her for protection, but she could not avoid constant street harassment and theft. During one incident, someone stole $1,000 from her on the sidewalk.
A decade of exposure took a permanent toll on her body.
“All these health issues I have now, I didn’t have,” Thomas said. “I got them all out here in the streets.”
Six months after moving into a private room through Pathway Home, Thomas finally has reliable electricity to power her oxygen machine and blood pressure monitor, store her heart medication in a refrigerator, and manage her health.

“Housing is an intervention to help with vascular problems—like leg swelling and open wounds from sleeping sitting up—because now our patients have a bed to elevate their legs and sleep,” said Kowalski, who has operated a mobile clinic van since December 2020. “From a medical standpoint, we can provide care, but housing is the key intervention to actually get people better.”
Homelessness advocates point to L.A. County’s high cost of living and the severe gap between fixed disability payments and local rents as key drivers fueling the region’s homelessness crisis.
In an emailed statement, the Inglewood Mayor’s Office cited the shelter operation at Hollywood Inn Suites, a converted motel on Century Boulevard, as a key local success in resolving encampments.
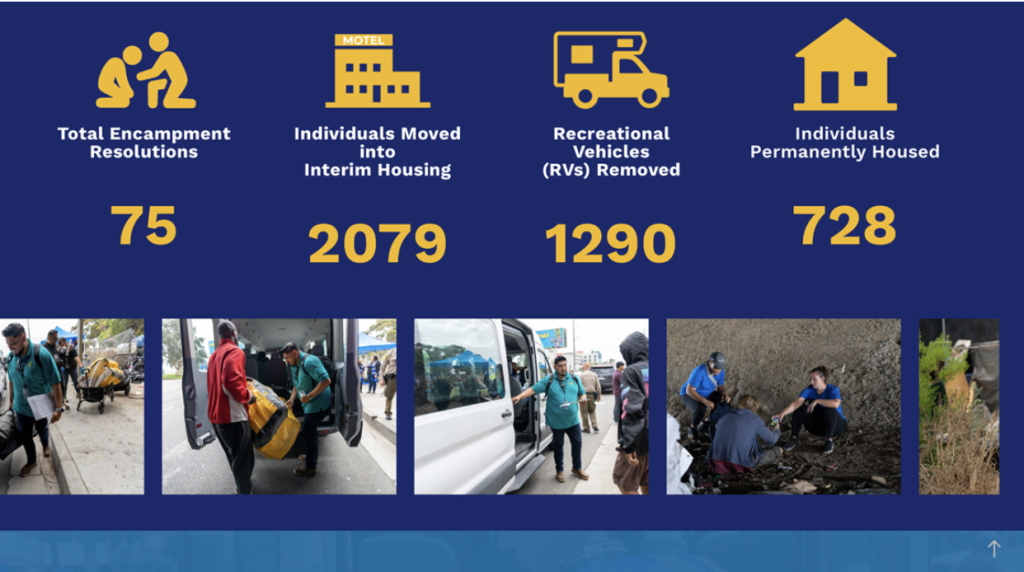
The city said its Pathway Home partnership with Los Angeles County housed 54 people who had been living on the streets. It is also exploring motel master leasing and said it would consider adding a homeless services coordinator, funded through Los Angeles County’s Measure A, in June 2026.
When discussing the types of housing initiatives like Pathway Home that place seniors into interim housing, Kushel emphasizes that a standard apartment is not enough since older adults need specific physical adaptations.
“A lot of the issues we’re having is just the physical design of whether there’s infrastructure for people who can’t climb stairs,” Kushel said. “There’s a physical design aspect like, are there grab bars, non-slip surfaces and night lights.”
For Ramirez and Thomas, moving off the streets into stable housing has allowed them to focus on long-term recovery, healthcare, and personal goals.

Ramirez, who rides his bicycle up to 100 miles a week, said he is rebuilding his strength while gathering the medical records needed to secure a housing voucher for a local senior complex through Pathway.
His dream is to one day reunite with his 23 grandchildren and 12 great-grandchildren.
“I just want to be with my grandkids, raise my great-grandkids, and jam with them, you know what I mean?” Ramirez said. “Being out on the street was rough, just fighting all the time. But since I’ve been here, you know, it’s been all right. I’m home.”
For Thomas, months inside interim housing under Pathway Home have provided a secure environment to manage her health. With her medical needs finally managed and her daily living environment secure, she is now looking toward the future—hoping to acquire a computer and take tax preparation courses to build new job skills.
It is a sharp departure from her years spent struggling just to survive on the streets.
“I’m not a hopeless case,” Thomas said. “This is just my new way of living, and I’m adjusting to it.”
Marion Apio
Marion Apio is a multimedia journalist from Uganda currently based in Inglewood reporting for the Observer Group Newspaper of Southern California in Los Angeles. She pursued journalism to make information more accessible—especially for underserved communities like the one she grew up in. Her reporting focuses on access to basic resources necessary to advance human rights, education, health and with a strong interest in solutions journalism that highlights working models addressing community-level challenges.
She is a California Local News Fellow, USC California Health Equity Fellow and Widening the Pipeline Fellow with National Press Foundation. Marion has reported for Richmond Confidential, Oakland North, Bloomberg, and has also worked with the Investigative Reporting Program at UC Berkeley on issues related to journalist safety and human rights.
Black Press
Street Medicine Brings Care to Unhoused Angelenos — But Housing Remains the Missing Prescription
BAKERSFIELD NEWS OBSERVER — Mobile street medicine teams treat the immediate health needs of the unhoused, but barriers to care, trauma, stigma and housing costs can leave the underlying causes of homelessness unresolved.
Marion Apio reported this story while participating in the USC Annenberg Center for Health Journalism’s 2026 California Health Equity Fellowship
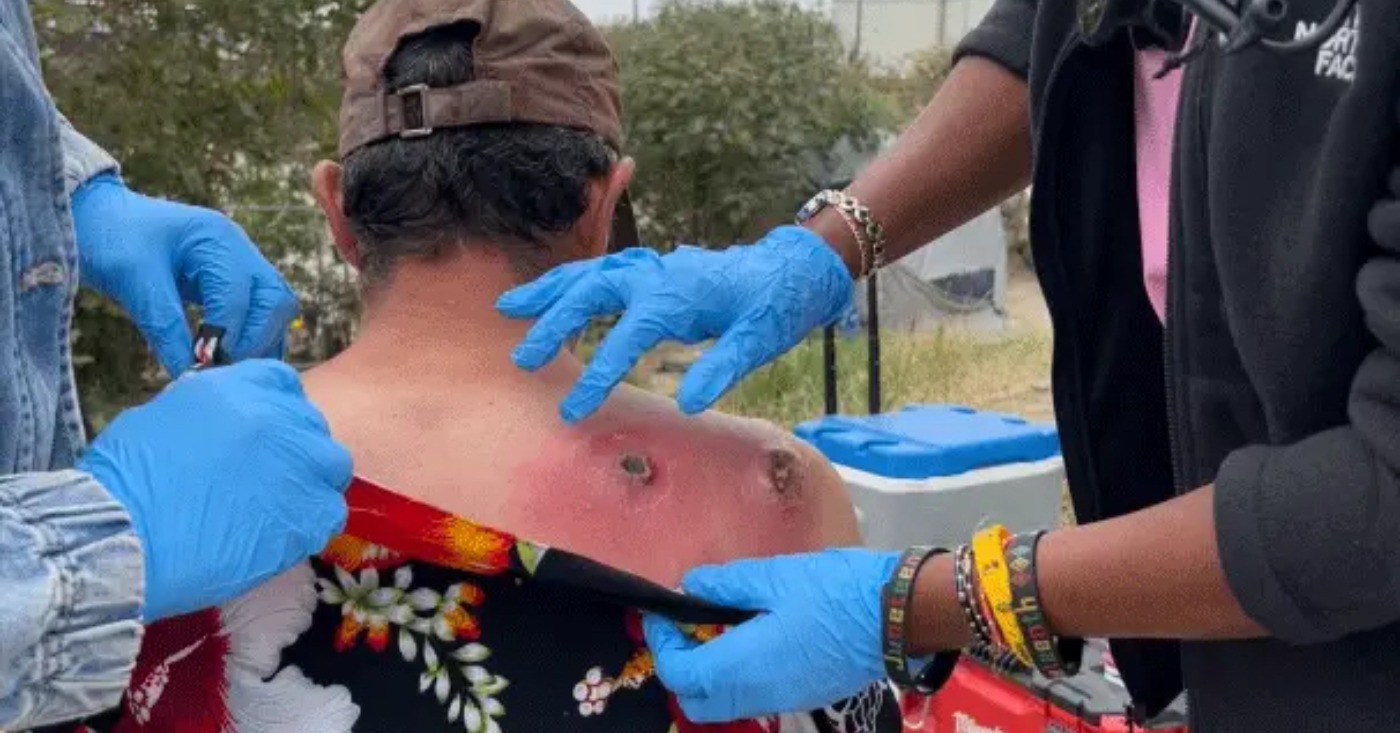
By the time a street medicine team met Alfred Flores last June along the Los Angeles River , two spider bites on his back had swollen with infection,untreated for three days.
Los Angeles News Observer
LA news from the Black press.
The stories Black Angelenos need, from people who live here. Free every Thursday.
Get the LANO Weekly
Free weekly newsletter. Unsubscribe anytime.
Divorced a year ago, the 53-year-old had been living along the riverbank for three years without a car or phone, making it difficult to connect with housing programs or reach a doctor as the infected wounds worsened with redness, heat, pus and pain.
On her weekly outreach along the L.A. River, Bukola Olusanya—a nurse practitioner and a street medicine provider with St. John’s Community Health—examined Flores on-site and wrote a prescription for antibiotics.
“My wound is infected,” Flores said in Spanish through an interpreter. “It is normal to be bitten by a spider in this area but I need help finding a home.”
Flores’s experience highlights the steep barriers to receiving housing support and providing medical care among people experiencing homelessness in Los Angeles. Many cannot access care because of physical or mental health conditions, or can’t connect to housing programs because they often lack a phone.
Traditional health care systems often require patients to have transportation, identification, a safe place to store medications and the ability to make follow-up appointments — barriers that can be difficult to overcome for people surviving on the streets.

Street medicine helps people whatever their circumstances
Street medicine challenges the traditional notion that health care must begin inside a medical facility, extending services to those in non-traditional settings and in urgent need.
These teams shift the delivery model by bringing health care directly to patients on the streets, rather than waiting for them to seek treatment in hospitals or clinics. They provide critical care that can stabilize health conditions while helping patients connect with benefits, housing and other services.
Jessica Sanchez, director of the Street Medicine team at St. John’s Community Health, said the program receives about $500,000 annually from L.A. Care Health Plan, $365,000 from the Federal Health Resources and Services Administration and $100,000 from the Los Angeles County Department of Public Health. The team also bills Medi-Cal for eligible medical services, though not all patients are insured or eligible for reimbursement.
Sanchez said the program’s grants typically run for three to five years, providing funding stability. The “street medicine initiative is not currently facing a funding threat,” she said.
Since 2023, St. John’s Community Health—a network of non-profit, federally qualified health centers—has deployed a multidisciplinary street medicine unit in Los Angeles. The mobile vans are staffed by a nurse practitioner, a medical assistant, a health benefits counselor, a community health worker, a behavioral health clinician, a substance abuse counselor and a driver.
The teams provides primary care, behavioral health, and benefits enrollment on the streets, reducing administrative hurdles to head off medical emergencies and reach unsheltered patients.
Primary care and connections are what street medicine can do best
The teams work Monday through Friday and serve around 320 patients a month.
They treat acute wounds, manage chronic conditions like diabetes and hypertension, conduct field blood draws, dispense medications, and connect patients to housing resources through the Los Angeles Homeless Services Authority’s Coordinated Entry System.
“Three years ago when we had just started street medicine it was with one team and one provider,” Olusanya said. “But with the increasing demand—especially after COVID—the team doubled everything.”
Deploying two teams is not enough without building trust with unhoused patients, Olusanya said, a lesson she learned on the beat.
While street medicine often can stabilize chronic conditions on the pavement, clinicians stress that field care is a vital shield, not a permanent solution. Without a locked door or a refrigerator to store insulin, medical intervention only acts as a Band-Aid while patients remain trapped in what can be seemingly endless housing queues.

Tanny Hernandez, 45, and her husband, Benwell Hernandez, 35, spent over three years living on the streets. They are now living in a temporary shelter in downtown Los Angeles.
Struggling to manage diabetes without refrigerated insulin
Until they encountered the St. John’s street medicine team, Tanny struggled to manage diabetes without a refrigerator to store her insulin, along with experiencing grand mal seizures and bone disease that forced her to use a wheelchair.
“My sugar levels were crazy—I mean, in the 400 range,” Tanny said. “I can’t be in direct sunlight, so I mean, everything was bad and it was going downhill.”
The American Diabetes Association recommends a premeal blood glucose target of 80 to 130 mg/dL for most nonpregnant adults with diabetes.
When unsheltered Angelenos seek traditional hospital care, they often face health struggles while navigating trauma from administrative hurdles and aggressive security in environments that can feel hostile rather than welcoming.
“While it may be tempting to think that mental health disorders or substance use cause homelessness, there is stronger evidence that the reverse is true,” said Kathryn Leifheit, an assistant professor of Health Policy and Management at the University of California, Los Angeles. “When people become homeless, housing insecurity causes severe mental strain that worsens health conditions over time.”
Homelessness remains at a crisis level in Southern California, mirroring national trends, Leifheit said. The insufficient supply of affordable housing puts many people at risk.
A rent increase can tip people already in crisis into homelessness, experts say
“When rents are high relative to incomes, any economic shock, life event, sudden illness or major bill can put someone at risk of becoming homeless,” Leifheit said.

This crisis carries a stark racial dimension. Black residents make up less than 10% of Los Angeles County’s population but accounted for about one-third of people experiencing homelessness in the Los Angeles Continuum of Care’s 2026 count, according to the Los Angeles Homeless Services Authority. The Continuum of Care is a federally designated network that coordinates homeless services and housing programs.
The count identified 21,822 Black people experiencing homelessness. Street medicine is an important way to access care for unhoused people of color, with 25% of street medicine patients identifying as Black and 23% identifying as Latino, according to the California Health Care Foundation.
“Black Americans have much lower family wealth and they’re much less likely to own their house because of redlining,” said Margot Kushel, Director of the UC San Francisco Benioff Homelessness and Housing Initiative. She points as a key contributor to “generations and generations of anti-Black racism and other ways to extract Black Americans out of the home ownership market.”

When Rayshawn Whittenburg, a 20-year-old Black Angeleno, encountered Olusanya and her team, she had spent six months on the streets with a high-risk pregnancy.
She was under the team’s care before her newborn inhaled amniotic fluid at birth, sending the infant to neonatal intensive care for two weeks. The baby was later released from the hospital into the care of Whittenburg’s mother.
“A stark racial dimension” to homelessness for Black Angelenos
Whittenburg’s experience highlights the severe maternal health disparities documented across Los Angeles County, where Black mothers and infants experience disproportionately high rates of life-threatening complications and mortality. For those surviving on the street, homelessness adds severe environmental stress and care delays to an already perilous baseline.
Whittenburg said she returned to the streets after losing her interim housing placement at the Los Angeles Inn because she did not realize that failing to remain continuously at the shelter would cost her a bed.
“I really keep to myself most of the time,” Whittenburg said. “I don’t really like people because it’s always drama.”

Olusanya noted that unsheltered patients routinely face judgment from healthcare providers based on their appearance or assumptions about drug use – preconceived notions she pushes back against, as most of her patients are not on the street because of addiction.
“One huge misconception is that unhoused folks are also inherently dangerous,” said Carol Ross, assistant director of Santa Monica outreach for The People Concern, a nonprofit that provides housing and supportive services. “Statistically speaking, folks with serious mental illness are much more of a danger to themselves than to others.”
After seven years of sobriety, Teff Ejigu, 37, is back on the streets navigating severe health and housing challenges.
Ejigu, who describes himself as a political science graduate, said he became unhoused after past triggers contributed to a relapse. He lost his housing six months ago and currently lacks a phone and essential documents to access benefits or housing such as a state ID and Social Security card.
“You know, we can’t give up,” Ejigu said. “I’m hoping that after I get back on my feet, I’ll be able to use this place as a launching pad to restarting my career and getting back to school.”

Navigating housing applications can be complicated and stressful
Beyond missing paperwork, navigating public benefit systems requires administrative literacy.
“There are resources out there, but you have to speak a special language to fill out all these forms,” Ross said. “People who don’t access public benefits have no idea how challenging it is. It’s like a full-time job.”
The main operational challenge for street medicine teams remains patient follow-up. Without phones or fixed addresses, patients are frequently lost to care, especially when encampments are cleared by the city. Olusanya said clinicians also encounter administrative barriers when trying to connect patients with services
Ross noted similar systemic limitations when patients face acute conditions, describing one unhoused individual struggling to receive cancer treatment—a case far more complex than treating a spider bite.
“In terms of getting folks connected to primary care, it works well, but there’s a lot of work to do in terms of linking people to higher levels of care,” Ross said.

“There’s definitely a need to be sure that street medicine is age friendly, that it has the workforce trained to deal with the unique needs of older adults…” Kushel said.
Local leaders should foot the bill for more street medicine teams, providers say
Some providers say city and county leaders could do more to strengthen mobile street units and cut red tape for permanent housing placements.
The Inglewood mayor’s office said the city is using federal, state and local funding to support affordable and supportive housing, including project-based vouchers and permanent supportive housing.”
The city said it is tracking 600 affordable units in various stages of predevelopment and monitoring about 46 existing density-bonus affordable units.
Roberto Chavez, HUD programs manager for the City of Inglewood, said the city is not equipped or funded to deploy mobile medical responses directly.
“I don’t think the city is equipped to deploy those resources because that’s more a function of the county or the state,” Chavez said. “We don’t have street medicine workers. That’s not something we receive funding for.”
Chavez noted that federal funding constraints continue to impact municipal budgets as housing costs outpace federal allocations.
“Every year costs go up for housing, right, and so the budget authority that we’re allocated from the federal government is not keeping up with that allocation,” Chavez said.
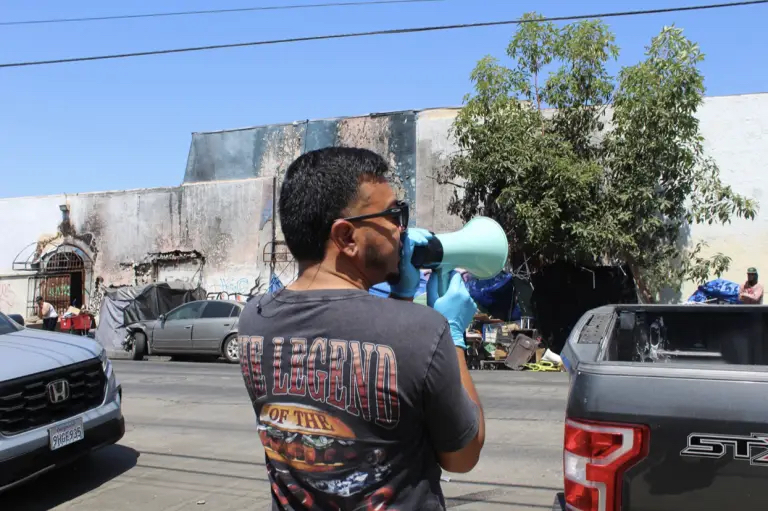
Off the streets, the next hurdle is going from temporary to permanent housing
The transition from temporary beds to permanent housing remains a challenge across the region. Across Los Angeles, the county identified the shortage of affordable permanent housing as the biggest barrier to moving people from interim to permanent housing.
“Healthcare is a human right. Just because somebody is living in an alley doesn’t mean that they don’t deserve to have a doctor who understands them,” said Ross.
“We only see some of them once or twice a week, so that’s the gap that we have,” Olusanya said of unhoused patients. “Cities have a bigger role to play. They have to provide the safety net that is needed by residents.” Health experts said when consistent clinical rapport and trust are established, street medicine can serve as a vital bridge to care.

“Street medicine doesn’t end homelessness. It is trying to keep people alive and safe while they’re homeless,” Kushel said. The street medicine team continues to care for Tanny and Benwell Hernandez, who live in temporary housing in downtown Los Angeles through the Inside Safe program. When Tanny cannot reach a pharmacy, the team delivers her medication directly to her door.
Regular health care “saved us,” one newly housed patient says
Benwell is studying to become a peer educator while the couple works to secure permanent housing. Still, their future remains uncertain.
Tanny said her biggest fear is waiting in temporary housing for six months only to end up back on the street.
Unlike patients living on the riverbank or sidewalk, Tanny can now benefit from reliable follow-up care because she now has a fixed address.
“We were at the point of giving up, but this program saved us,” Tanny said. “With what they do for me, my whole body—like my internal system—feels like it’s slowly getting better.”
Marion Apio
Marion Apio is a multimedia journalist from Uganda currently based in Inglewood reporting for the Observer Group Newspaper of Southern California in Los Angeles. She pursued journalism to make information more accessible—especially for underserved communities like the one she grew up in. Her reporting focuses on access to basic resources necessary to advance human rights, education, health and with a strong interest in solutions journalism that highlights working models addressing community-level challenges.
She is a California Local News Fellow, USC California Health Equity Fellow and Widening the Pipeline Fellow with National Press Foundation. Marion has reported for Richmond Confidential, Oakland North, Bloomberg, and has also worked with the Investigative Reporting Program at UC Berkeley on issues related to journalist safety and human rights.
Black Press
OP-ED: Washington Has a Chance to Save Veterans’ Lives
BLACKPRESSUSA NEWSWIRE — I became paralyzed watching young Marines go outside the base, thinking about their families and whether they would see them again. I began hallucinating that wounded Marines I cared for were walking toward me in the war zone. I now recognize that, alongside my own PTSD, I was carrying secondary PTSD from caring for wounded Marines.

I graduated from Marine Corps boot camp a couple weeks before September 11, 2001. I had no idea how profoundly 9/11 would change the trajectory of my life.
I went on to deploy to Iraq and Afghanistan. Between deployments, I worked at the Wounded Warrior Battalion in San Diego, supporting Marines as they rebuilt their lives. What I did not understand was how deeply I was absorbing their grief and losses.
That became clearer when I later deployed to Afghanistan during one of the deadliest periods of the war for Marines. I purposefully stopped counting the flag-draped coffins as they were loaded onto planes to return home, swallowing my grief so I could return to the mission.
I became paralyzed watching young Marines go outside the base, thinking about their families and whether they would see them again. I began hallucinating that wounded Marines I cared for were walking toward me in the war zone. I now recognize that, alongside my own PTSD, I was carrying secondary PTSD from caring for wounded Marines.
With every loss, I swallowed what I felt just to keep functioning. I kept moving forward, until everything I buried became impossible to ignore.
I did not recognize what was happening until five years after returning home. I sought help. Therapy helped me feel less alone, but my symptoms continued to affect my life and relationships.
My experience is not unique. 870,000 veterans receiving VA health care were diagnosed with PTSD in 2024. Since 9/11, nearly 150,000 veterans have died by suicide. Many continue searching for relief after available treatments have failed.
That is why veterans are cautiously hopeful about psychedelic treatments.
Studies of psilocybin for treatment-resistant depression show significant reductions in depressive symptoms, with up to one-third of patients achieving remission in some trials. Research involving veterans with PTSD found that 75% were in remission one month after psilocybin treatment.
I followed the research before pursuing psilocybin treatment myself. During that experience, I was finally able to access the grief I spent decades burying. It did not erase what happened or the memories of the Marines I lost. It changed my relationship with those memories. They no longer controlled my life.
I reconnected to the self I had lost and was able to feel joy and love again.
Psychedelic medicines are not a cure-all. But veterans pursuing them are not looking for shortcuts. Many have spent years doing everything the medical system asked while continuing to search for relief.
Our government is beginning to recognize the potential of new approaches.
This year, President Trump signed an executive order to accelerate research and reduce barriers to psychedelic treatments for serious mental illness. VA is conducting clinical trials of MDMA for PTSD and psilocybin for depression. In July, FDA finalized guidance for clinical trials involving psychedelic drugs.
If these treatments receive FDA approval, the healthcare system must be ready to deliver them responsibly — through DEA action, clear safeguards, and VA facilities prepared to provide care.
Our country asks a great deal of those who serve. If evidence demonstrates that these treatments are safe and effective, veterans should not wait years longer because Washington failed to prepare for success.
Juliana Mercer is a Marine Corps veteran and executive director of Healing Breakthrough. A version of this column was published in Stars and Stripes.
Black Press
TILGHMAN: Why Parents of Children with IEPs Should Know Their School Bus Driver
WASHINGTON INFORMER — Parents of children with Individualized Education Programs (IEPs) often face unique considerations regarding their child’s school transportation. Ensuring consistency and understanding their child’s needs on the bus can be a significant concern.

As the father of a young daughter with autism, I have learned that getting your child to school is not always as simple as putting them on the bus and waiting for them to come home.
When your child has an Individualized Education Program, you pay attention to things other parents may never have to think about.
Who is working with my child today? Does this person understand her needs? What happens if her routine suddenly changes? If something goes wrong and she cannot fully explain it to me, who will be able to tell me what happened?
Those questions do not stop at the schoolhouse door. They follow our children onto the school bus.
That is why one of the simplest pieces of advice I can give another parent of a child with an IEP is this: Get to know your child’s bus driver and attendant.
Learn their names. Introduce yourself. Say good morning. Ask how your child is doing on the ride.
Those few minutes can matter more than we realize.
For some children with disabilities, consistency is incredibly important. The same bus, the same driver, the same seat and the same routine can provide a sense of comfort before the school day even begins.
Then one morning, something changes.
The bus is late. There is a substitute driver. The route changes. The bus does not arrive when expected.
For many families, that is an inconvenience. For some of our children, it can change the entire morning.
As parents, we also know that our children may not always come home and tell us exactly what happened during the ride. That makes the adults who interact with them even more important.
A bus driver may notice that your child suddenly does not want to get on the bus. An attendant may notice that your child seems upset at the same point along the route every day.
They may notice a change in behavior, a problem with another student, or simply that something seems different.
That information can be valuable to a parent.
But relationships work both ways.
Parents can also help transportation staff understand our children. You do not have to share every detail of your child’s disability or educational record. But appropriate information about communication, behavior, safety or transitions can help the adults responsible for transporting your child better understand how to support them.
And when a transportation problem occurs, you are no longer starting the conversation with a complete stranger.
That does not mean parents should be responsible for fixing school transportation. We shouldn’t.
School systems remain responsible for providing required transportation services, including services identified in a student’s IEP. When buses are repeatedly late, accommodations are not being followed or transportation problems interfere with a child’s education, parents should document those concerns and raise them with the appropriate school and transportation officials.
Building a relationship with a driver should complement accountability, not replace it.
That distinction is important.
As a father navigating special education, I have learned that advocacy is not only about what happens during an IEP meeting.
Advocacy happens in the hallway. It happens at pickup. It happens through an email to a teacher. And sometimes it happens at the bus stop at 7 o’clock in the morning.
Our children’s educational experience begins before they enter the classroom and continues after they leave it.
Think about the person behind the wheel.
For some children, their bus driver is the first school employee they see every morning and the last one they see every afternoon.
That person is part of your child’s school experience.
So tomorrow morning, if you haven’t already, introduce yourself.
Learn the driver’s name.
Let them learn your child’s name — and, when appropriate, a little about what helps your child succeed.
It won’t prevent every late bus, substitute driver or transportation problem.
But if there is one thing I continue to learn as both a father and an advocate, it is that relationships matter.
And for children with IEPs, one more adult who knows, understands, and cares about your child can make a difference.
Based on reporting by Washington Informer.
Black Press
Partnership Helps Patients Prepare for Medicaid Rules
ST. LOUIS AMERICAN — Affinia Healthcare and Employment Connection have partnered to assist patients in securing employment, training, or volunteer opportunities. This collaboration comes as new Medicaid work requirements are set to begin on January 1, 2027. These requirements will mandate certain adults to meet work, education, or community service criteria to maintain their coverage, though some exemptions may apply.

Affinia Healthcare and Employment Connection are teaming up to help patients find jobs, training or volunteer opportunities as new Medicaid work requirements approach.
Beginning Jan. 1, 2027, certain adults will have to meet work, education or community service requirements to keep their coverage. Some patients may qualify for exemptions.
Patients seeking assistance can call Affinia Healthcare at 314-814-8700 and ask about the partnership. Affinia’s outreach team can help connect them with Employment Connection.
The post Partnership helps patients prepare for Medicaid rules appeared first on St. Louis American.
Based on reporting by St. Louis American.


Defender Athlete Interview – John Rangel

Defender Athlete Interview – Elijah Eche

Inside a Century of Black Press Archives

The Defender Goes One on One with Congressman Christian Menefee

Demystifying the Retail Installment Sale Contract: Your Guide #shorts

CalAIM Helped Alfred Flores Rebuild His Life. Why Can’t More Californians Access Its Benefits?

Kia Seltos: Advanced Safety & Tech Features Explained #shorts

How Inglewood’s Homeless Seniors Are Finding Relief Through Housing and Trauma-Informed Care

Carmen Meeks Turns Teachers’ Lessons Into a Legacy | 2026 Education Salute

Street Medicine Brings Care to Unhoused Angelenos — But Housing Remains the Missing Prescription

Women Learned Their Jail Strip Searches Were Recorded. Their Outrage Changed the Law

Latest Massacre in Haiti Reveals Cruelty U.S. Deportations

Black Americans Have Doubts About the U.S. Food System

When Praises Go Up: SUGC Nominated for Prestigious Stellar Award.

Booked and Unbound: The Legacy of Black Women’s Literary Circles

U.S. Sole Nation to Oppose U.N. Resolution Correcting Africa’s Size on World Maps

Prostate Cancer is Twice as Likely to Kill Black Men. Talking to Your Doctor Could Help Save Your Life

Outnumbered: Elbert Cox’s Equation for Greatness

COMMENTARY: Big Mama Said ‘Don’t Let Grief Break the Bank’

U.S. Open Influencers Spark Backlash over Ring Lights, Filming as Gauff and Osaka Speak Out
Defender Athlete Interview – John Rangel
Defender Athlete Interview – Elijah Eche
Inside a Century of Black Press Archives
The Defender Goes One on One with Congressman Christian Menefee
Demystifying the Retail Installment Sale Contract: Your Guide #shorts
Kia Seltos: Advanced Safety & Tech Features Explained #shorts
Carmen Meeks Turns Teachers’ Lessons Into a Legacy | 2026 Education Salute

2 Crucial Bolt EV Interior Details You MUST Inspect! #shorts

California Becomes First State to Require Slavery-Ties Disclosure 📱

California Becomes First State to Require Slavery-Ties Disclosure
-

 Black History1 week ago
Passing for White, Fighting for Black America: The Courage of Walter White
-

 Black History1 week ago
The Youngest American Killed in the Vietnam War
-

 Black History4 days ago
Remembering Chauncey Bailey as Student Journalists Face Threats to Truth-Telling
-

 Black Press1 week ago
Mayor Lee Announces $1 Million Kaiser Permanente Grant for Pilot Program to Address Homelessness, Clean Up Public Spaces throughout Oakland
-

 Art1 week ago
Peter Magubane: a Camera Against Apartheid
-

 Black Press1 week ago
OP-ED: How Head Start Also Helps Parents
